
SHARE Knowledge Hub
Lifestyle Health Checks
A workplace lifestyle health check is an optional, clinically governed wellbeing offer. Individual results belong with the person and provider, with a clear private follow-up route. The employer should address work-design barriers and receive only genuinely anonymous aggregate learning where appropriate. It must keep this programme separate from exposure-driven health surveillance and capability decisions.
Understanding Lifestyle Health Checks
A workplace lifestyle health check is an optional, clinically governed wellbeing offer. Individual results belong with the person and provider, with a clear private follow-up route. The employer should address work-design barriers and receive only genuinely anonymous aggregate learning where appropriate. It must keep this programme separate from exposure-driven health surveillance and capability decisions.
Why this matters at work
Potential benefits include earlier awareness of raised blood pressure, cholesterol or diabetes risk, access to smoking or weight support, and engagement by groups less likely to attend conventional services. Benefit depends on accurate testing, understandable communication and completed follow-up rather than the number of checks performed.
Workplace power changes the context. People may feel observed or fear that results affect promotion, attendance or redundancy. Location, manager involvement, visible queues and team-level reporting can reveal participation or health information even if the form says confidential.
How organisations manage this in practice
Aggregate reporting can show service reach, common risk factors and referral demand without revealing individuals. It is not anonymous merely because names are removed. Small teams, rare conditions, exact ages and combined categories can make people identifiable. Agree a disclosure-control standard before reporting: minimum cell size, suppression, category grouping, rounding and limits on cross-tabulation. Do not give managers ad hoc cuts of data to identify who might need encouragement. Report measures relevant to programme improvement, such as invitation reach, uptake, completed components, result delivery, referral route and access barriers. Avoid league tables that blame teams for risk profiles influenced by age, deprivation or job pattern. Anonymisation should be tested by people with knowledge of the workforce context.
Agree useful aggregate questions and suppress or combine small groups where identities could be inferred. Avoid reporting a condition against a team with one or two members. Review participation, access barriers and follow-up quality rather than treating uptake as a performance target. Keep identifiable clinical information with the authorised provider and document the lawful, necessary sharing arrangements.
Point-of-care testing brings clinical measurement into a workplace or mobile clinic, but portability does not reduce quality requirements. Maintain an equipment register with manufacturer, model, identifier, validated use, software, maintenance, calibration or verification, consumables and responsible clinical lead.
What boundary should lifestyle health checks have?
This page gives general workplace wellbeing guidance, not medical, legal or HR advice.
Lifestyle health checks can help people notice risk factors and seek support earlier, but they should not become a workplace diagnosis tool. A blood pressure reading, cholesterol result or diabetes-risk score needs proper clinical interpretation and follow-up. A line manager should not interpret a result or use it to make assumptions about performance, attendance or capability.
The workplace role is to create supportive conditions: time to attend voluntary checks, signposting to NHS or GP routes, fair access, privacy, and improvements to work factors such as breaks, hydration, shift patterns, welfare, food access, sedentary time and stress. Where work ability, safety-critical duties or adjustments are uncertain, occupational health or qualified advice should be used.
Voluntary
Participation should normally be optional and based on clear information.
Confidential
Individual results should be handled by health professionals, not casually by managers.
Supportive
Use checks to signpost and improve wellbeing support, not to judge people.
Separate
Keep wellbeing checks distinct from statutory health surveillance and fitness-for-work decisions.
What are the key facts about lifestyle health checks?
The most important facts are about purpose, consent, confidentiality and follow-up.
Many risks are silent
Blood pressure, cholesterol or diabetes risk may not cause obvious symptoms.
Screening is not diagnosis
Results need competent interpretation and follow-up.
Privacy is central
Health data is special category data and must be handled carefully.
Aggregate data may help
Anonymous trends can guide wellbeing campaigns without exposing individuals.
Avoid shame
Messaging should not judge weight, appearance, age, health status or lifestyle.
Work factors matter
Shift work, breaks, toilet access, food options, fatigue and stress can affect health choices.
What are lifestyle health checks in plain English?
They are optional checks that can help people understand health risk factors and decide whether to seek further advice.
A lifestyle health check might include questions or measurements about blood pressure, cholesterol, diabetes risk, smoking, alcohol, movement, diet, sleep or general wellbeing. It may be delivered through the NHS, a GP, occupational health, a public-health provider or a workplace wellbeing campaign.
The value is awareness and signposting. The risk is overreach. If a workplace asks for too much information, shares results badly, pressures people to attend or links health results to employment decisions, trust can collapse quickly.
| Element | Good meaning | Poor use |
|---|---|---|
| Purpose | Help people understand risk and access support. | Screen people for performance or attendance decisions. |
| Participation | Voluntary and clearly explained. | Mandatory without a lawful reason. |
| Results | Private to the individual and clinical provider. | Shared with managers or teams. |
| Follow-up | Signpost to NHS, GP, OH or wellbeing support. | Leave people anxious with unexplained results. |
| Workplace learning | Use anonymous trends to improve campaigns. | Name or target individuals. |
What checks may be included?
The content of a check should match the provider, clinical governance and purpose.
Common checks include blood pressure, cholesterol, diabetes risk, body measurements, lifestyle questions, smoking and alcohol questions, physical activity, sleep, mental wellbeing and signposting. Some workplace programmes also include vision, hearing or musculoskeletal screens, but these should not be confused with statutory health surveillance.
A health check should not promise certainty. A normal result can be reassuring but does not remove the need to seek help for symptoms. An abnormal result does not automatically mean a diagnosis, but it does need a clear route for follow-up.
| Check | What it may indicate | Workplace boundary |
|---|---|---|
| Blood pressure | Raised cardiovascular risk. | Signpost to NHS/GP; do not ask for details. |
| Cholesterol | Cardiovascular risk factor. | Clinical interpretation needed. |
| Diabetes risk | Risk factors for type 2 diabetes. | Offer signposting and reasonable support. |
| Movement/activity | Sedentary time and activity habits. | Encourage inclusion, not fitness judgement. |
| Sleep and fatigue | Wellbeing and safety-critical concerns. | Review work patterns where relevant. |
| Smoking/alcohol questions | Health-risk behaviours. | Keep confidential and non-disciplinary unless safety impairment arises. |
| Mental wellbeing | Stress, mood or support needs. | Use private signposting and avoid diagnosis. |
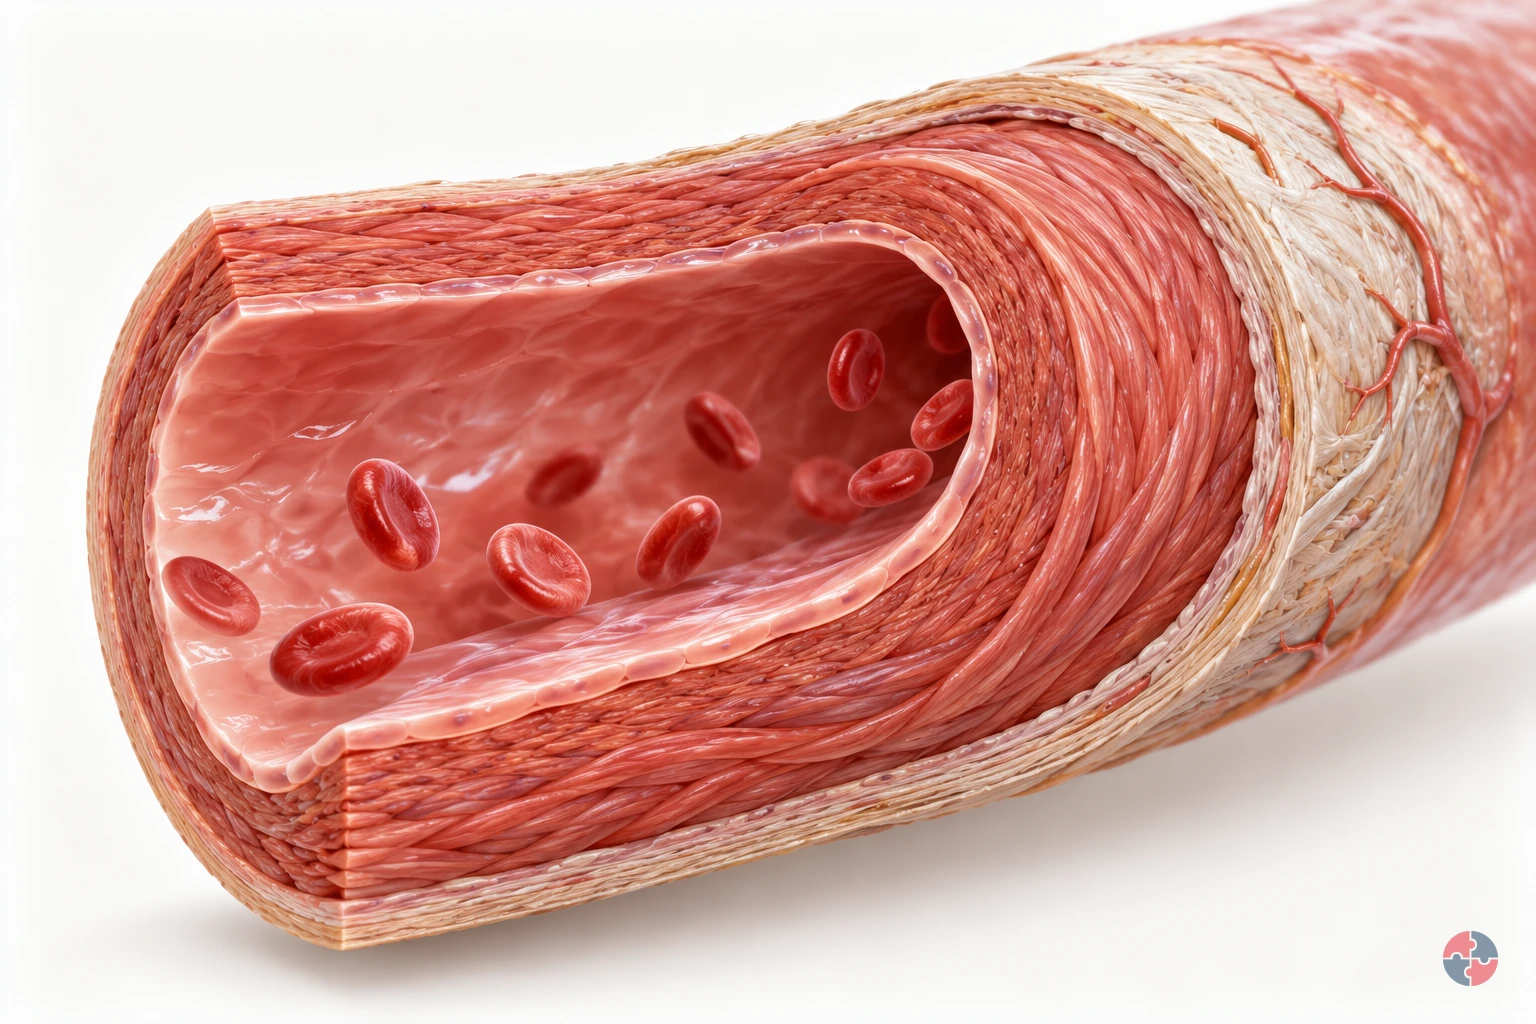

What do blood pressure numbers mean, and how can persistent high pressure affect the heart and organs?
Interactive anatomy · Blood pressure and possible long-term effects · Updated 2026-10-23
Read all anatomy and process explanations without the viewer
Fixed adult educational content; no user readings, health profiles or medication information. Diagnosis, personalised treatment targets or medication changes Pressure inferred from pulse, anxiety, smartwatch or device measurements Personal cardiovascular risk or time-to-disease calculations Pregnancy, children, frailty and specialist-condition management Reassurance from one reading or symptoms being absent The model does not measure blood pressure or generate a physiological waveform.
Systolic pressure
The first, higher number is pressure when the heart pumps. In the fixed 120/80 mmHg teaching example, 120 is systolic. This example is not a personal treatment target. NHS: Blood pressure test
Diastolic pressure
The second, lower number is pressure between heartbeats. In the fixed example, 80 mmHg is diastolic: pressure during relaxation between beats. NHS: Blood pressure test
Artery wall
Arterial walls normally stretch as pressure changes. The artery wall surrounds the lumen, the space carrying blood. It accommodates the pressure associated with circulation, and its structure is different from a deposit inside a vessel. The enlarged layers help locate the wall but do not measure its thickness or stiffness. Compare this label with the lumen before reading the pressure-phase explanation. Wye Valley NHS Trust: High blood pressure — cardiac rehabilitation
Vessel lumen
The inside space carries blood. Pressure acts against the surrounding wall. A lumen is not the same structure as a wall deposit or surrounding tissue. Wye Valley NHS Trust: High blood pressure — cardiac rehabilitation · Manchester University NHS Foundation Trust: Blood Vessels
Heart
Persistently raised pressure makes the heart work harder. Heart muscle may thicken or become less efficient over time. This is a possible effect, not an inevitable sequence after one high reading. University Hospitals of Leicester NHS Trust: Hypertension (high blood pressure) · St George’s University Hospitals NHS Foundation Trust: Heart health and cancer treatment — high blood pressure context
Brain circulation
High pressure can increase stroke risk. The map highlights the brain’s blood supply, not a predicted stroke or an individual diagnosis. NHS: High blood pressure
Kidney vessels
High pressure and kidney problems can affect each other. Pressure can strain small kidney vessels. Kidney disease can also raise pressure through fluid and hormonal effects. NHS: Chronic kidney disease · NHS MyHealth London: Kidney Health
Eye circulation
Vessels in the eyes can be affected. The eye card explains a possible effect of persistent high pressure. Selecting it does not imply that the learner has retinal damage. NHS: High blood pressure · University Hospitals of Leicester NHS Trust: Hypertension (high blood pressure)
Cuff measurement
A properly performed check measures blood pressure. A real cuff is used to obtain a blood-pressure reading; this illustrated cuff only displays a fixed teaching example. It receives no device data and cannot tell how the learner’s pressure changes. Feeling well does not reliably establish that pressure is normal. Use the display to understand the two-number format, keeping personal assessment separate. NHS: Blood pressure test · NHS: High blood pressure
Repeated readings
Further readings are normally needed to establish the pattern. A clinician may arrange home, repeated clinic or ambulatory monitoring. Do not diagnose or dismiss a raised value from this animation. NHS: Blood pressure test · NHS: High blood pressure · NHS MyHealth Devon: Hypertension — measurement context and repeat assessment
Open the complete process transcript
The process, step by step
Locate wall and lumen
Start with the artery’s wall and the lumen, the open space inside it that carries blood. Pressure acts against the surrounding wall; the wall and the moving blood are not the same structure. Compare the two labels before moving to the beat-phase example. This enlarged cutaway helps locate the parts being discussed, but its thickness and shape are illustrative. It does not measure stiffness, narrowing or a person’s blood pressure. Following the labels first gives the later pressure numbers a physical context instead of presenting them as unrelated figures. Wye Valley NHS Trust: High blood pressure — cardiac rehabilitation · Manchester University NHS Foundation Trust: Blood Vessels
What to watch: Find the open lumen inside the artery and the surrounding wall, checking the boundary between the two labelled regions.
Why it matters: Blood pressure describes pressure against vessel walls. Locating the wall and lumen helps keep a pressure reading distinct from a picture of narrowing, wall thickness or a deposit inside a vessel.
Explore this step: Select the wall and lumen in turn and describe the different structure identified by each label.
Pressure during pumping
Select the systolic label and relate it to the heart’s pumping phase. Systolic pressure is the higher number in a blood-pressure reading. In this fixed teaching example it is 120 mmHg. The number belongs to the example, rather than being measured from the learner or calculated by the illustration. Read it together with the phase label, then compare it with the between-beats step. The purpose is to connect a familiar written number with the phase it describes, not to set a personal treatment target or interpret an individual result. NHS: Blood pressure test
What to watch: Locate the systolic label and the higher number in the fixed display, relating both to the pumping phase described beside them.
Why it matters: A blood-pressure result describes more than one phase of the heartbeat. Identifying the systolic phase helps the learner understand what the first number represents without using this illustration to judge their own pressure.
Explore this step: Read the systolic label aloud with its unit, then explain which phase of the heartbeat it describes.
Pressure between beats
Now select diastolic pressure and compare it with the pumping phase. Diastolic is the lower number, describing pressure while the heart relaxes between beats. The fixed example shows 80 mmHg. Relaxation between beats is part of the repeating cycle; it does not mean the pressure reading is zero or that the circulation has stopped. Keep the two phase labels in view as you compare them. The illustration provides a way to understand the terms and their order, without measuring a person, setting a target or offering a diagnosis. NHS: Blood pressure test
What to watch: Locate the diastolic label and the lower number, then compare it with the systolic label from the previous step.
Why it matters: The lower number describes a different phase from the higher number. Understanding both prevents “between beats” being mistaken for no pressure and keeps the two-number reading connected to the heartbeat cycle.
Explore this step: Compare both labels and explain why the second number describes a different phase from the first.
Read two numbers
Bring the two labels together in the illustrated cuff display: systolic first and diastolic second, both expressed in millimetres of mercury, written mmHg. The fixed reading is 120/80 mmHg. The slash separates the two pressure values; it is not a division exercise. Follow each number back to its phase label so the display has meaning. This cuff illustration receives no device data and takes no reading. It teaches how a result is written, while interpretation and any personal follow-up remain outside the model. NHS: Blood pressure test
What to watch: Compare the first and second numbers on the illustrated cuff display with their systolic and diastolic labels and the shared unit.
Why it matters: Reading both numbers with the unit preserves their meaning. It avoids treating one isolated number, an illustrated cuff or the appearance of the model as a complete assessment of someone’s blood pressure.
Explore this step: Point to each number, name its phase and read the complete example with the unit mmHg.
Understand context and follow-up
Blood pressure varies, so a reading needs context rather than being judged from this single fixed illustration. A healthcare professional may arrange repeated measurements or monitoring outside the clinic to understand the pattern. Select the repeated-readings label and compare it with the one example shown on the display. The model does not record a diary, analyse a trend or decide which follow-up a person needs. Its role is to explain why a measurement and an interpretation are different things, while the existing professional follow-up guidance remains the next point of reference. NHS: Blood pressure test · NHS: High blood pressure · NHS MyHealth Devon: Hypertension — measurement context and repeat assessment
What to watch: Locate the repeated-readings label and compare it with the single fixed cuff example, noticing the different questions they address.
Why it matters: A fixed teaching example cannot establish a person’s usual pressure. Considering context and follow-up keeps the learning activity separate from diagnosis and avoids either dismissing or diagnosing a raised result from the model.
Explore this step: Explain the difference between recognising the two-number format and assessing a person’s pattern of readings.
Explore possible longer-term effects
Open the organ map and explore the heart, brain, kidney and eye labels one at a time. Persistent high pressure can place strain on vessels and organs and increase the risk of serious health problems. The cards identify possible longer-term effects; they are not inevitable stages after one high reading. Compare each card with the artery-wall view to connect the wider subject with the structure introduced at the start. The model cannot show whether damage is present in any person, and completing the map is not a screening test. NHS: High blood pressure · NHS: Chronic kidney disease · University Hospitals of Leicester NHS Trust: Hypertension (high blood pressure)
What to watch: Select the heart, brain, kidney and eye cards separately, then compare their explanations with the artery-wall label.
Why it matters: The importance of a pressure check is not limited to the number itself. The map explains possible consequences without implying that every organ is affected, that symptoms must be present or that the model can diagnose damage.
Explore this step: Choose two organ cards and explain why the map describes possibilities rather than a diagnosis or inevitable sequence.
Read the practice situations and all answer explanations
Sources and how the model is made
The opening images are AI-generated anatomical illustrations. The interactive 3D models and labelled SVG diagrams use original procedural artwork. These teaching images are not medical scans or diagnostic tools. Source references support the learner explanations and do not grant artwork rights.
- NHS: Blood pressure test — Reviewed November 2025: systolic/diastolic meanings, mmHg, cuff checks, repeat readings, clinic/home context. No personalised target or measurement input.
- NHS: High blood pressure — Often no symptoms, professional follow-up, affected organs, emergency chest symptoms and general care/prevention.
- Wye Valley NHS Trust: High blood pressure — cardiac rehabilitation — Normal arterial stretch and possible stiffness/narrowing with persistent high pressure. Replaces a non-NHS vessel-mechanism link.
- NHS MyHealth Devon: Hypertension — measurement context and repeat assessment — Narrow use for clinic versus home/daytime-average confirmation and variation. Some other treatment/alcohol/severe-threshold text is older and is explicitly not reused; current national NHS sources control advice.
- NHS: Chronic kidney disease — High pressure can strain small kidney vessels and contribute to kidney disease. No staging or treatment simulation.
- University Hospitals of Leicester NHS Trust: Hypertension (high blood pressure) — Long-term pressure load and possible heart, kidney, brain and sight effects; qualitative ventricular hypertrophy context only.
- St George’s University Hospitals NHS Foundation Trust: Heart health and cancer treatment — high blood pressure context — Narrow normal-pressure mechanism point: high blood pressure can cause heart muscle stiffening or thickening over time. No oncology/arrhythmia treatment advice transferred.
- NHS MyHealth London: Kidney Health — Kidney/pressure effects can be bidirectional through fluid and hormonal function. No personal medication or diet recommendation.
- NHS South East Clinical Senate: Blood pressure — Clinical Senate background information — Indexed primary document supports systolic and/or diastolic threshold logic. Direct PDF retrieval failed; recheck at clinical sign-off. No treatment protocol copied.
- Manchester University NHS Foundation Trust: Blood Vessels — Basic vessel structure and lumen/flow context, not pressure diagnosis.
How does the NHS Health Check fit in?
The NHS Health Check is an England public-health programme, not an employer wellbeing test.
NHS Health Check information describes an invitation every five years for eligible adults aged 40–74 without specified existing conditions. Eligibility and access depend on the NHS programme; a workplace provider cannot label a similar campaign as an NHS Health Check without being part of that route. Workers in Scotland, Wales or Northern Ireland need locally relevant NHS signposting rather than an assumption of programme availability.
An employer may publicise the official NHS route and remove practical barriers to attendance, such as inflexible hours. The employer does not need to know who was invited or a person’s result.
| Question | NHS Health Check | Workplace offer | Direct source |
|---|---|---|---|
| Where? | England public-health programme. | Location and provider must be stated honestly. | NHS Health Check |
| Who? | Eligible adults 40–74, generally every five years, subject to exclusions. | Participation should be truly optional and fair. | NHS eligibility |
| Who sees results? | The person and relevant NHS clinical route. | The person/provider; employer gets no individual result by default. | ICO worker-health data |
How can the hierarchy of controls reduce work-related health risks before relying on lifestyle checks?
A workplace should use checks to support wellbeing and improve conditions, not to police lifestyle.
A good programme might reveal that night-shift workers struggle to access healthy food, drivers lack toilet breaks, warehouse teams have poor hydration access, office workers are sedentary, or supervisors need confidence to signpost mental wellbeing support. The organisation can then improve the environment rather than telling individuals to try harder.
This is where SHARE-style thinking matters. The useful output is not a pile of personal test results. It is a better welfare plan, communications plan, campaign calendar, manager training package, adjustment route and review of work factors that make healthy choices harder.
Where shift work, breaks, heat or food access contribute to a work-related risk, apply ERICPD to that work-design hazard rather than to a person’s weight or diagnosis: eliminate an avoidable night shift where feasible; reduce hours or intensity; isolate a hot task; engineer rest/cooling facilities; set protected breaks; provide task-suitable PPE for residual hazard; and keep those controls checked. The five-level hierarchy still starts with elimination, substitution, engineering and administrative controls before PPE. These are examples requiring a task risk assessment, not a prescription to change an individual’s lifestyle.
Five-level analogy: design a voluntary check without privacy harm
The hazard is pressure to participate or disclosure of identifiable health information, not a person’s lifestyle. Remove employer access to individual clinical results; use a provider-held result and aggregate feedback only where a small group cannot be identified. Put secure booking and access controls in place, then give a plain notice explaining purpose, genuine choice, who receives data and how to decline. PPE has no role in this data risk. The programme owner checks the provider agreement, sample report and access permissions before launch, then tests whether managers can see only the agreed information. An NHS Health Check is an England health-service programme, not an employer fitness assessment. Sources: NHS Health Check; Workers’ health information.
ERICPD response: a small-team result may identify someone
Stop the disclosure and remove the unnecessary report. Reduce the information held to what is needed for the programme, isolate access to authorised staff, and control any incident through the organisation’s data-protection route. PPE is inapplicable. Sustain the control by checking future report thresholds, provider permissions and manager practice; do not blame the worker who noticed the problem. The privacy lead records the decision and permits a revised aggregate report only after a re-identification check. A manager must not ask who declined a check or treat a result as fitness for work. Sources: Worker health monitoring; Workers’ health information.
| Outcome | Example | Evidence |
|---|---|---|
| Better signposting | Clear routes to NHS, GP, OH, EAP and local support. | Intranet page and campaign materials. |
| Improved welfare | More accessible water, toilets, rest areas and food storage. | Welfare inspection and worker feedback. |
| Shift support | Healthy food access and breaks for night workers. | Shift review and canteen/vending changes. |
| Manager confidence | Managers know how to have private support conversations. | Training records and case-review quality. |
| Aggregate learning | Anonymous trends inform wellbeing campaigns. | Provider report with no unnecessary personal data. |
| Inclusion | Campaign materials avoid stigma and are accessible. | Equality impact review. |
How can the ERICPD hierarchy of controls reduce work-related health risks before relying on lifestyle checks?

| ERICPD control level | Topic-specific example | Source and full task context |
|---|---|---|
| Eliminate | Remove unnecessary employer access to individual health results. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Reduce | Minimise information and use a suitable provider-held results route. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Isolate | Restrict access to authorised staff. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Control | Explain genuine choice and use non-identifying aggregate reports. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| PPE | PPE has no role in this privacy risk. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Discipline | Review permissions and report thresholds before disclosure. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
How can the ISO 45001 hierarchy of controls reduce work-related health risks before relying on lifestyle checks?

| ERICPD control level | Topic-specific example | Source and full task context |
|---|---|---|
| Eliminate | Remove unnecessary employer access to individual health results. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Reduce | Minimise information and use a suitable provider-held results route. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Isolate | Restrict access to authorised staff. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Control | Explain genuine choice and use non-identifying aggregate reports. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| PPE | PPE has no role in this privacy risk. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
| Discipline | Review permissions and report thresholds before disclosure. | Read the full task example, checks and stop points on this page. NHS Health Check · Workers’ health information · Worker health monitoring |
How should consent, confidentiality and data protection work?
Separate consent to the clinical check from the employer’s lawful basis and special-category condition for any health-data processing.
ICO worker-health monitoring guidance says consent is rarely an appropriate UK GDPR lawful basis in employment because of the power imbalance. A genuinely optional wellness offer with no negative consequence for refusal may allow consent to be considered, but the organisation must still identify a lawful basis and special-category condition. ICO worker-health information guidance explains purpose limitation, minimisation and access controls.
Before launch, tell workers who the provider is, what is measured, what the provider retains, who receives results, the retention period and the private follow-up path. A manager must not see blood pressure, cholesterol, diagnoses or named attendance unless a separate, necessary and lawful process is justified. Small-group “anonymous” statistics may identify people, so suppress them.
| Decision | Programme design | Failure trigger | Direct source |
|---|---|---|---|
| Voluntary choice | No penalty, incentive pressure or manager challenge for refusal. | Pause campaign if choice is not real. | ICO consent boundary |
| Clinical results | Give results and follow-up to individual/provider. | Stop employer access to raw results. | ICO minimisation |
| Employer learning | Share only adequately anonymised themes at safe group sizes. | Suppress identifying slices. | ICO worker-health information |
| Data basis | Document lawful basis and special-category condition before collection. | Do not collect until reviewed. | ICO health monitoring |
Before collection, the programme owner and privacy lead map the data flows, determine each party’s actual controller/processor role and the required agreement, document the lawful basis and special-category condition, set retention and test access permissions. Record the DPIA decision: likely high-risk processing requires one and ICO recommends assessing this sensitive context; not every small campaign automatically needs a DPIA. ICO marks its worker-health guidance under review after the Data (Use and Access) Act; check its current notice at each programme review without treating the core privacy obligations as suspended.
Illustrative disclosure test: an overall report covers 40 people, but the night-shift total, a role breakdown and last month’s report together reveal one participant’s result to a manager who knows the rota. Review overlapping cuts, totals, repeat releases and recipient knowledge; suppress, combine or withhold results if people remain identifiable. There is no universally safe headcount that makes data anonymous.
How are lifestyle checks different from health surveillance?
General wellbeing checks cannot replace legally required, exposure-driven health surveillance.
HSE COSHH health-surveillance guidance explicitly distinguishes surveillance from general health screening and promotion. Surveillance is a planned scheme to detect work-related effects where its criteria apply; it supports action on the workplace exposure. A voluntary blood-pressure day is not an isocyanate respiratory scheme, a noise hearing programme or a lead medical-surveillance route.
If the risk assessment shows a surveillance duty, arrange the specific competent scheme and act on control findings. Keep its records, legal basis and worker information separate from a wellbeing campaign.
| Dimension | Lifestyle check | Health surveillance | Direct source |
|---|---|---|---|
| Trigger | Voluntary wellbeing offer. | Work exposure and residual disease risk. | HSE surveillance |
| Aim | Personal awareness and clinical signposting. | Early detection of work-related effect and control review. | HSE surveillance purpose |
| Employer response | Improve work conditions and access, without individual results. | Investigate exposure and apply required controls. | HSE control action |
How should lifestyle checks stay separate from surveillance, capability and performance?
Lifestyle checks should remain voluntary wellbeing support unless a separate, lawful and properly governed process is triggered.
This distinction should be repeated in campaign material, provider instructions and manager training: lifestyle checks are voluntary wellbeing support; health surveillance is exposure or risk-driven; occupational health advice is used when work and health need competent interpretation; and performance or capability decisions require a fair HR process, not a raw health-check result.
A workplace should therefore avoid the quiet drift where a wellbeing provider collects results, managers ask who attended, HR stores values in personnel files and supervisors begin linking health scores to absence or productivity. That drift damages trust and may create data protection, equality and employment-relations problems.
| Boundary | Keep it as | Do not let it become |
|---|---|---|
| Purpose | Awareness, signposting and supportive wellbeing. | Screening people for suitability, attendance risk or productivity. |
| Participation | Voluntary, informed and free from pressure. | Mandatory attendance unless a separate lawful process applies. |
| Data access | Private results for the individual and health provider. | Manager-accessible records or team comparisons. |
| Employer learning | Anonymous aggregate themes at a safe group size. | Named risk lists or small-group reports that identify people. |
| Management action | Improve welfare, breaks, support routes and campaign design. | Use results to trigger disciplinary, performance or capability action. |
| Work ability concern | Use occupational health, HR and fair process where genuinely needed. | Ask line managers to interpret test values or diagnosis labels. |
| Health surveillance | Keep separate when work exposure creates a legal/risk-driven need. | Replace statutory surveillance with a general wellbeing check. |
What are the benefits and risks of workplace health checks?
Good programmes can help; poor programmes can damage trust.
The benefits are strongest when checks are voluntary, confidential, clinically governed and linked to useful follow-up. They can help people notice silent risk factors, access support earlier and feel that the employer cares about wellbeing.
The risks are real. Poorly designed programmes can shame people, collect excessive data, create anxiety, confuse screening with diagnosis, overlook work factors, discriminate, or give false reassurance. The programme owner should explain both benefits and limitations before people choose whether to take part.
| Potential benefit | How to secure it | Risk if poorly managed |
|---|---|---|
| Early awareness | Use competent checks and clear follow-up. | Unexplained results create anxiety. |
| Better signposting | Link to NHS, GP, OH and local services. | Workers are left with leaflets only. |
| Wellbeing engagement | Use inclusive, non-judgemental language. | People feel blamed or targeted. |
| Aggregate insight | Use anonymous trends. | Named data damages trust. |
| Work design improvement | Act on break, welfare, shift and food-access barriers. | Focus only on personal behaviour. |
| Support for adjustments | Use private conversations and OH advice. | Managers pry into medical detail. |
What real workplace scenarios show good use of health checks?
A voluntary health check helps only when the worker controls participation and private results, while the employer acts on work conditions it can change.
A workplace health-check campaign should adapt to real conditions. The same message will not work equally for office workers, night-shift workers, drivers, outdoor workers, mobile engineers and lone workers.
The best programmes ask what the workplace can change. If drivers cannot access toilets, a hydration campaign will fail. If night-shift workers only have vending machines, a healthy eating message can sound hollow. If staff fear monitoring, health checks will be avoided.
| Scenario | Useful support | What to avoid |
|---|---|---|
| Night-shift worker | Healthy food access, rest breaks, fatigue support and signposting. | Telling people to eat better while canteen is closed. |
| Driver or mobile worker | Toilet planning, hydration points, appointment flexibility and private signposting. | Productivity controls that restrict toilet breaks. |
| Office worker with stress symptoms | Private conversation, workload review and NHS/EAP signposting. | Assuming a health-check score explains performance. |
| Outdoor construction team | Welfare, water, shade, breaks and campaign materials in briefings. | Weight-loss campaign during heavy heat exposure. |
| Worker needing adjustments | Ask about work barriers and consider OH/HR advice. | Requesting diagnosis details casually. |
| Culturally diverse workforce | Inclusive food, language and access considerations. | One-size-fits-all diet advice. |
What should managers do and avoid?
Managers should support work barriers, not interpret test results.
A manager can remove work barriers, explain how to use the voluntary offer and privately agree a change to hours or facilities. The provider handles individual results. If a worker asks for a work adjustment, record only the restriction or support needed, its owner and review date; use occupational health for clinical interpretation where appropriate. ICO worker-health guidance supports limiting employer access to necessary information.
| Do | Do not | Why |
|---|---|---|
| Explain voluntary support routes. | Pressure people to attend checks. | Consent and trust matter. |
| Ask what work is making health harder. | Ask for unnecessary diagnosis or test details. | Focus on function and support. |
| Signpost to NHS, GP, OH or EAP. | Give personal medical advice. | Managers are not clinicians. |
| Consider reasonable adjustments. | Assume health status from age, size or appearance. | Avoid discrimination and stereotypes. |
| Record agreed support and review dates. | Record raw health-check results in routine notes. | Minimise health data. |
| Escalate safety-critical uncertainty to OH/HR. | Ignore possible impairment or fatigue risks. | Balance privacy with safety. |
How can this support a wellbeing campaign?
A good campaign makes healthier choices easier without judging people.
Campaign design should start with worker voice: what makes healthy choices difficult here? The answer might be break timing, food access, shift length, workload, facilities, cost, language, caring responsibilities, culture, transport or fear of stigma.
The campaign can then combine optional health checks with practical workplace improvements: walking groups, healthier food options, hydration points, sleep and fatigue education, blood pressure awareness, signposting to NHS Health Check, smoking support, financial wellbeing and manager conversation training.
| Prompt | Good practice | Evidence |
|---|---|---|
| Purpose | Define awareness, signposting and work-support goals. | Campaign brief. |
| Worker voice | Ask what barriers exist in real shifts and roles. | Survey/focus group summary. |
| Provider governance | Check competence, follow-up, privacy and clinical governance. | Provider due diligence. |
| Inclusion | Use accessible language and avoid judgement. | Equality/inclusion review. |
| Workplace action | Improve welfare, breaks and support routes. | Action tracker. |
| Review | Use aggregate feedback and participation learning. | Anonymous report and management review. |
Name the provider’s clinical owner and give participants a reachable private contact, a result-explanation method and urgent-versus-routine referral arrangements before the first check. Rehearse an unexpected finding without sending raw results to a manager. The clinician sets test-specific thresholds and follow-up; the employer verifies that the private route works.
What records should a workplace keep?
Record the programme and support decisions, not unnecessary personal health detail.
For general health checks, the employer usually needs records showing campaign governance, provider due diligence, privacy notices, communications, aggregate outcomes, actions taken and review. Individual clinical results should normally stay with the person and healthcare provider.
If a worker asks for support, record the agreed work adjustment, owner, review date and any occupational-health recommendation that the worker understands is being shared. Keep diagnostic detail out unless clearly necessary and lawful.
| Record | Purpose | Do not include |
|---|---|---|
| Campaign brief | Purpose, audience, provider and follow-up. | Named health results. |
| Privacy information | Explain data use before checks. | Vague 'wellbeing data' wording. |
| Provider due diligence | Competence, governance and insurance. | Marketing claims only. |
| Aggregate report | Anonymous trends and learning. | Small-group data that identifies people. |
| Action tracker | Workplace improvements after campaign. | Personal medical values. |
| Adjustment record | Support agreed with individual. | Unnecessary diagnosis detail. |
What workplace boundaries should employers understand?
Apply the legal route for the work location and test the actual controls, responsibilities and records.
Great Britain and Northern Ireland have distinct primary and management regulations. Official guidance helps interpret practical arrangements, but is not a replacement for the applicable instrument. Specialist legal advice is needed for a disputed duty or enforcement decision.
| Jurisdiction | Direct instrument or guidance | Operational decision supported |
|---|---|---|
| Great Britain | Health and Safety at Work etc. Act 1974 | General employer, worker and public protection duties. |
| Northern Ireland | Health and Safety at Work (NI) Order 1978 | The separate NI general-duty route. |
| Great Britain | Management of Health and Safety at Work Regulations 1999 | Risk assessment, arrangements, competence and emergency planning. |
| Northern Ireland | Management of Health and Safety at Work Regulations (NI) 2000 | The separate NI management and risk-assessment route. |
| United Kingdom | ICO worker-health data guidance | Lawful basis, special-category condition, minimisation and access. |
| Great Britain | Equality Act 2010 | GB disability discrimination and reasonable-adjustment route. |
| Northern Ireland | ECNI Disability Code of Practice | Separate NI disability and adjustment route under the DDA. |
How could Riverside Leisure Ltd manage this in practice?

Riverside Leisure Ltd would use lifestyle health checks as a voluntary wellbeing campaign, not as a test of employee value.
Riverside Leisure Ltd is a leisure and community employer with lifeguards, gym staff, cleaners, reception teams, cafe workers and mobile maintenance staff. It wants to promote health without overreaching into personal medical life.
| Management element | How the business would manage it | Evidence to review |
|---|---|---|
| Assessing | Riverside asks workers what makes healthy routines difficult across shifts, public-facing work and mobile maintenance. | Anonymous worker feedback and role map. |
| Analysing | It separates health-promotion checks from occupational health, fitness-for-work and statutory surveillance. | Wellbeing governance note. |
| Implementing | Optional checks are delivered by a competent provider with clear consent, private results and NHS/GP signposting. | Provider contract and privacy notice. |
| Checking | Managers receive aggregate themes only and review welfare, breaks, water, food access and shift support. | Aggregate report and action tracker. |
| Learning | The business improves rest breaks, noticeboards, healthy food access and manager training without collecting raw results. | Campaign review and improvement log. |
What training or awareness supports lifestyle health checks?
Training should help people understand checks, privacy and supportive conversations.
Training should be role-based. General awareness creates a baseline, but supervisors, managers, advisers and senior leaders need different levels of decision-making, verification and escalation competence.
Give managers a practical exercise: a worker declines a check and another asks for an adjustment. The assessor looks for a clear voluntary offer, no adverse consequence, a confidential referral, and an action on relevant work conditions. Record the observed decision and repeat the exercise when the programme, provider or data flow changes; attendance at an awareness session is not evidence of competence.
| Training level | Who needs it | What it should cover |
|---|---|---|
| General awareness | Everyone who may encounter the topic. | Plain-English awareness of lifestyle health checks, why it matters, common situations, basic controls, reporting routes and where to get help. |
| Topical practical training | Workers most directly involved in the task or support process. | Task examples, control expectations, warning signs, stop-work points, escalation and records. |
| Supervisor and manager training | People allocating work, authorising tasks, holding conversations or checking controls. | Decision quality, private conversations, supervision, risk assessment, evidence, escalation and review. |
| Specialist or competent-person training | Wellbeing leads, HR, occupational health, line managers, data protection leads and senior sponsors who design or commission health-check activity. | Provider clinical governance, privacy, inclusion, result explanation and referral competence, with occupational-health and legal/privacy support where needed. |
| Refresher and learning | People in roles where drift, rare tasks or changing work creates risk. | Scenario refreshers, incident learning, audit findings, drills, reassessment and updates after change. |
How should managers review voluntary health-check programmes?
Assign a decision owner, test whether the actual work control works and act on failures before returning to the task.
A programme owner should define the purpose of an optional health check, the provider’s role, what managers may see and how workers can raise concerns. Check the actual access permissions and sample reports before launch, then review whether the programme is producing pressure or unintended disclosure. An optional check does not decide fitness for a task.
HSE management guidance supports the Great Britain management route; HSENI health and safety made simple provides the Northern Ireland route. The task-specific sources elsewhere on this page govern the particular exposure or adjustment decision.
What warning signs show health checks are poorly designed?
Warning signs usually involve pressure, privacy weakness, judgemental messaging or no follow-up.
Warning signs are included because failure usually appears before a serious event. Treat these points as prompts for inspection, audit, supervision and management review rather than as simple compliance statements.
| Warning sign | What it suggests | Action |
|---|---|---|
| Managers ask for results | Privacy boundary is weak. | Reset data-sharing rules and brief managers. |
| Attendance is pressured | Consent may not be freely given. | Make voluntary nature clear. |
| Campaign focuses on weight or appearance | Stigma and exclusion risk. | Use health, energy, support and access language. |
| No referral route | Screening may create anxiety without benefit. | Confirm NHS/GP/OH signposting. |
| Small-team aggregate reports | People may be identifiable. | Aggregate at a safe level or do not share. |
| Health checks replace workplace controls | Employer shifts burden onto individuals. | Review work design, welfare and risk factors. |
| Results used in capability decisions | Potential discrimination and trust failure. | Use OH/HR route and lawful, proportionate evidence. |
Which acronyms and terms are useful for lifestyle health checks?
These terms keep programme participation, privacy and legal surveillance separate.
| Term | Meaning | Use here |
|---|---|---|
| NHS | National Health Service | The NHS Health Check is an England programme. |
| ICO | Information Commissioner’s Office | UK data protection regulator. |
| UK GDPR | United Kingdom General Data Protection Regulation | Employer processing needs a lawful basis; health data also needs a special-category condition. |
| OH | Occupational health | Competent advice on work and health, distinct from a general campaign. |
| COSHH | Control of Substances Hazardous to Health | Exposure-driven surveillance where criteria are met. |
| ERICPD | Eliminate, Reduce, Isolate, Control, PPE, Discipline | Apply to a real work-design hazard, not a person’s diagnosis. |
| Aggregate data | Grouped programme information | Must be truly anonymous before employer access. |
Unlock another resource
You have used this month’s two free downloads. Publish a post in your own words to unlock one more resource, or choose SHARE Individual for 10 downloads per month.
You decide whether to share. If you do, use the relevant platform disclosure tools and do not make claims you do not genuinely hold.