SHARE Knowledge Hub
Isocyanate Asthma
Isocyanate asthma is work-related asthma that can develop after exposure to reactive isocyanates in paints, coatings, foams or adhesives. Spraying can create inhalable mist, while skin contact may also contribute to sensitisation. Once sensitised, a worker may react to small further exposures; employers must prevent exposure, verify booth and respiratory controls, use appropriate health surveillance and respond promptly to symptoms without asking managers to diagnose them.
Understanding Isocyanate Asthma
Isocyanate asthma is a preventable occupational disease associated especially with inhaling spray mist from two-pack polyurethane paints, but exposure also arises from some foams, glues, coatings, flooring products and heated or disturbed polyurethane processes. An isocyanate-containing product can be water-based. A worker can inhale invisible mist even when the visible fan has disappeared, and a well-ventilated enclosure does not clear instantly.
Why this matters at work
Occupational asthma is asthma caused by exposure at work. Isocyanates may sensitise the respiratory system so that later exposures trigger inflammation and variable airway narrowing. Wheeze, chest tightness, breathlessness and cough may appear after work, at night or in the early morning. Rhinitis and eye irritation may precede lower-airway symptoms. Continued exposure after early symptoms can worsen prognosis.
COSHH requires prevention of exposure where reasonably practicable and otherwise adequate control, with special attention to substances capable of causing occupational asthma. Control at source takes priority over reliance on behaviour or RPE. A workplace exposure limit, where one applies, is not permission to cause sensitisation below that limit; HSE describes exposure to asthmagens as needing reduction as low as reasonably practicable.
How organisations manage this in practice
Define action boundaries before sampling. A failed pressure indication, loss of extraction, damaged breathing-air supply or uncertainty about measured clearance should stop spraying and prevent entry until a competent person restores and verifies the barrier. An abnormal biological-monitoring result should trigger prompt review of sampling timing, task, product, BA use, air supply, clearance and possible exposure of others. A symptom report needs prompt health assessment and exposure control even if the most recent urine result was below the guidance value.
For an adhesive bead or small pour, elimination or product substitution and controlled dispensing may be stronger controls than large-scale RPE. For spray foam or floor coatings, assess aerosol, ventilation, nearby trades, cure period and access control. The HSE construction pages provide task-relevant guidance, but a site must still evaluate its own process and product data.
Refresh competence after new products, equipment, exposure findings or observed drift. Include temporary and contractor workers in the same system. Check that people can explain when they must not spray, what they do if air supply fails, and how they report symptoms promptly.
How can I practise this topic in 3D?


Booth 1: isocyanate spray mist

Two-pack coating and isocyanate mist
All related inspection points 3 across 2 locations
Garage workshop 2 inspection points
Aerosystems Engineering 1 inspection point
Practice in the SHAREhub environment. Browser practice is separate from workplace competence and formal learning records.
What health boundary should readers understand?
This page is workplace guidance, not medical diagnosis or treatment advice.
Best-practice guide: Isocyanate Asthma

What health boundary should readers understand?
This page is workplace guidance, not medical diagnosis or treatment advice. Isocyanate asthma is work-related asthma that can develop after exposure to reactive isocyanates in paints, coatings, foams or adhesives.
Turn isocyanate asthma knowledge into a decision
Isocyanate asthma is work-related asthma that can develop after exposure to reactive isocyanates in paints, coatings, foams or adhesives. Spraying can create inhalable mist, while skin contact may also contribute to sensitisation. Keep product/SDS, substitution decision, booth test and clearance evidence, RPE/air-supply checks, biological-monitoring review, confidential health route and restart record.
Two-pack spray paint repair in a bodyshop
During spraying and mist clearance, keep the air-fed protection on and the booth access controlled; do not lift the visor in the mist. A competent manager checks the fault and exposure pathway, arranges health advice for the worker, and restarts only after controls and clearance arrangements are verified.
Airborne isocyanate can sensitise the airways
Spraying or other isocyanate work can create airborne exposure. Inhaled material can cause sensitisation and occupational asthma. Symptoms and failed control signals need prompt action and the appropriate clinical route. Use the full topic for the detailed mechanism, task limits and source scope.
Choose controls for isocyanate asthma
Elimination: Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits. Substitution: Validate a suitable isocyanate-free coating or non-spray process, checking performance and other hazards. Engineering controls: Restrict the spray area and prevent other workers entering during spraying and the verified clearance period. Engineering controls: Use a suitable maintained spray booth/room with effective extraction; verify containment and the measured clearance arrangement. Administrative controls: Follow the approved spraying and exit/entry procedure, keep required training current and arrange appropriate exposure monitoring and health surveillance. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Use the full isocyanate asthma lesson
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.

Read all six steps as text
1. What health boundary should readers understand?
This page is workplace guidance, not medical diagnosis or treatment advice.
- Avoid / redesign: Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits.
- Control the task: Restrict the spray area and prevent other workers entering during spraying and the verified clearance period.
- Verify before release: If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls.
This page is workplace guidance, not medical diagnosis or treatment advice. Isocyanate asthma is work-related asthma that can develop after exposure to reactive isocyanates in paints, coatings, foams or adhesives.
Apply it: Which part of this plan would you check at the workface before authorising the task?
2. Turn isocyanate asthma knowledge into a decision
Use the evidence to improve the actual work arrangement.
- Change at source: Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits.
- Make it observable: If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls.
- Keep useful evidence: Keep product/SDS, substitution decision, booth test and clearance evidence, RPE/air-supply checks, biological-monitoring review, confidential health route and restart record.
Isocyanate asthma is work-related asthma that can develop after exposure to reactive isocyanates in paints, coatings, foams or adhesives. Spraying can create inhalable mist, while skin contact may also contribute to sensitisation. Keep product/SDS, substitution decision, booth test and clearance evidence, RPE/air-supply checks, biological-monitoring review, confidential health route and restart record.
Apply it: What evidence would show that the change improves this task, rather than only completing a record?
3. Two-pack spray paint repair in a bodyshop
Example: a practical application of the existing topic lesson.
- Setting: A painter prepares a vehicle panel for two-pack isocyanate paint in an enclosed spray booth; a neighbouring worker may enter during booth clearance.
- Act: Before spraying, consider an isocyanate-free coating or non-spray method if the specification permits; otherwise verify booth extraction, air-fed respiratory protection and the task COSHH assessment.
- Hold / review: Stop if booth flow or supplied air fails, the product is unknown, a bystander enters, the visor is lifted in mist or symptoms are reported.
During spraying and mist clearance, keep the air-fed protection on and the booth access controlled; do not lift the visor in the mist. A competent manager checks the fault and exposure pathway, arranges health advice for the worker, and restarts only after controls and clearance arrangements are verified.
Apply it: At which point would you hold this example, and what evidence would allow it to proceed?
4. Airborne isocyanate can sensitise the airways
Connect the task, the route to the person and the control that can fail.
- Release: Spraying or other isocyanate work can create airborne exposure.
- Breathing: Inhaled material can cause sensitisation and occupational asthma.
- Repeat exposure: Symptoms and failed control signals need prompt action and the appropriate clinical route.
Spraying or other isocyanate work can create airborne exposure. Inhaled material can cause sensitisation and occupational asthma. Symptoms and failed control signals need prompt action and the appropriate clinical route. Use the full topic for the detailed mechanism, task limits and source scope.
Apply it: Where is this harm route present in the actual work, and which control breaks it before anyone is exposed?
5. Choose controls for isocyanate asthma
Start with the stronger practicable options and verify their effect.
- Elimination: Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits.
- Substitution: Validate a suitable isocyanate-free coating or non-spray process, checking performance and other hazards.
- Engineering controls: Restrict the spray area and prevent other workers entering during spraying and the verified clearance period.
- Engineering controls: Use a suitable maintained spray booth/room with effective extraction; verify containment and the measured clearance arrangement.
- Administrative controls: Follow the approved spraying and exit/entry procedure, keep required training current and arrange appropriate exposure monitoring and health surveillance.
Elimination: Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits. Substitution: Validate a suitable isocyanate-free coating or non-spray process, checking performance and other hazards. Engineering controls: Restrict the spray area and prevent other workers entering during spraying and the verified clearance period. Engineering controls: Use a suitable maintained spray booth/room with effective extraction; verify containment and the measured clearance arrangement. Administrative controls: Follow the approved spraying and exit/entry procedure, keep required training current and arrange appropriate exposure monitoring and health surveillance. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Apply it: Which stronger option can be used here, and who will verify it before accepting the remaining risk?
6. Use the full isocyanate asthma lesson
Follow the official sources below and retain the task-specific evidence.
- Official guidance: HSE - Isocyanates in construction
- Official guidance: HSG276 - Isocyanate paint spraying
- Task decision: Keep product/SDS, substitution decision, booth test and clearance evidence, RPE/air-supply checks, biological-monitoring review, confidential health route and restart record.
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.
Apply it: Which official source and full-topic section will you use to resolve the next decision?
Managers should not diagnose asthma, decide that wheeze is unrelated to work or allow continued exposure after credible symptoms without review. Isocyanate sensitisation can have life-changing consequences, and early recognition matters.
Workers with chest tightness, wheeze, persistent cough, breathlessness or symptoms that appear after work, in the evening or early morning should report promptly and be signposted to occupational health or medical advice. Severe breathing difficulty should be handled through first-aid and emergency arrangements.
- Breathing symptoms — Record exposure details and refer through OH/medical route. Treating symptoms as ordinary flu or poor fitness.
- Possible sensitisation — Remove or prevent further exposure pending competent advice. Re-exposing worker to test if symptoms recur.
- Health surveillance — Use competent occupational health arrangements. Line manager collecting detailed medical notes.
- Biological monitoring — Use results to check control effectiveness. Using results to blame workers without checking controls.
- Confidentiality — Record work restrictions and controls appropriately. Sharing health details with the team.
What are the key facts about isocyanate asthma?
The key message is that sensitisation prevention must come before symptoms appear.
An isocyanate product can be hazardous in a bodyshop, on a construction site or in a manufacturing task. A two-pack spray job needs product identification, a suitable booth, air-fed respiratory protection, clearance-time control and exposure/health checks. Symptoms can be delayed or improve away from work, so apparent recovery after a shift is not evidence that controls worked. See HSE - Isocyanates in construction; HSG276 - Isocyanate paint spraying.
Isocyanates are potent respiratory sensitisers
Exposure can cause occupational asthma and dermatitis.
Spraying creates invisible mist
Mist can be inhaled and can remain in spray areas until clearance is complete.
Air-fed BA is critical for spraying
Workers should not lift visors while mist is present.
Biological monitoring checks reality
Urine testing can show whether exposure controls are actually working.
Health surveillance is not optional where risk remains
It helps detect early signs so action can be taken before severe disease develops.
What is isocyanate asthma in plain English?
It is asthma caused by the immune system becoming sensitised to isocyanates at work.
Isocyanates are chemicals used in many polyurethane-based products. They are found in 2-pack paints, vehicle refinishing, spray coatings, foams, adhesives, resins and some construction products. Exposure can occur through inhaling aerosol, vapour or mist, and through skin contact with some products. See HSE - Isocyanates in construction.
Once a worker becomes sensitised, very small exposures may trigger asthma symptoms. This is why control cannot depend on whether the worker feels fine today. It must depend on preventing exposure, monitoring whether controls work and acting early on symptoms.
- Respiratory sensitiser — A substance that can cause allergic-type asthma after exposure. Exposure must be kept as low as reasonably practicable.
- 2K paint — Two-pack paint often containing isocyanate hardener. Common bodyshop and spray risk.
- Aerosol mist — Fine droplets generated by spraying. Can be invisible and inhaled deeply.
- Clearance time — Time needed for spray booth/room air to clear after spraying. Workers must keep BA on until safe to remove.
- Biological monitoring — Urine test indicating whether exposure occurred. Checks real-world control effectiveness.
Where are isocyanate exposures found?
Isocyanates are not limited to vehicle paint shops; they appear across industries and products.
The classic high-risk example is motor vehicle repair using 2K spray paints, but other exposures include construction spraying, floor screeds, adhesives, insulation foam, polyurethane manufacture, coatings, lacquers, resins and maintenance work on cured or uncured products.
The risk is greatest where products are sprayed or heated, where ventilation is poor, where workers work close to the source, where bystanders are nearby, or where people clean spray guns and equipment without proper controls.
- 2K vehicle paint spraying — High aerosol mist exposure. Spray booth, air-fed BA, clearance time and monitoring.
- Construction spray coatings — Mist may drift and expose others. Enclosure, exclusion and wind/ventilation planning.
- Foam and polyurethane work — MDI/TDI exposure possible depending on product. COSHH assessment and skin/respiratory controls.
- Adhesives/resins/floor screeds — Exposure may be less obvious than spraying. Product identification, ventilation and gloves/RPE.
- Spray gun cleaning — Can create significant exposure after main spray task. Controlled cleaning method and RPE.
- Bystander work — Others may enter before area is clear. Access control and clearance-time signage.
How does sensitisation happen?
Sensitisation means the body becomes unusually reactive after exposure.
The mechanism matters because the first serious warning may not occur during the first exposure. A worker can become sensitised over time, then later react to very small amounts. Symptoms may appear after work or during the night, so workplaces must ask about timing and patterns, not only what happens during the shift. See HSE - Isocyanates in construction.
Skin exposure may also matter. Poor glove selection, contaminated coveralls, poor cleaning and touching contaminated surfaces can contribute to overall risk and dermatitis.
- Latency — Symptoms may develop after a period of exposure. Do not assume early symptom-free work is safe.
- Delayed symptoms — Symptoms can appear hours after work. Health surveillance should ask about evening/early-morning symptoms.
- Tiny triggers — After sensitisation, low exposure may trigger asthma. Prevent further exposure pending competent advice.
- Skin and respiratory risk — Isocyanates can affect breathing and skin. Use respiratory and skin health surveillance where relevant.
- Control reliance — RPE behaviour and booth clearance can make or break control. Supervise and biologically monitor.
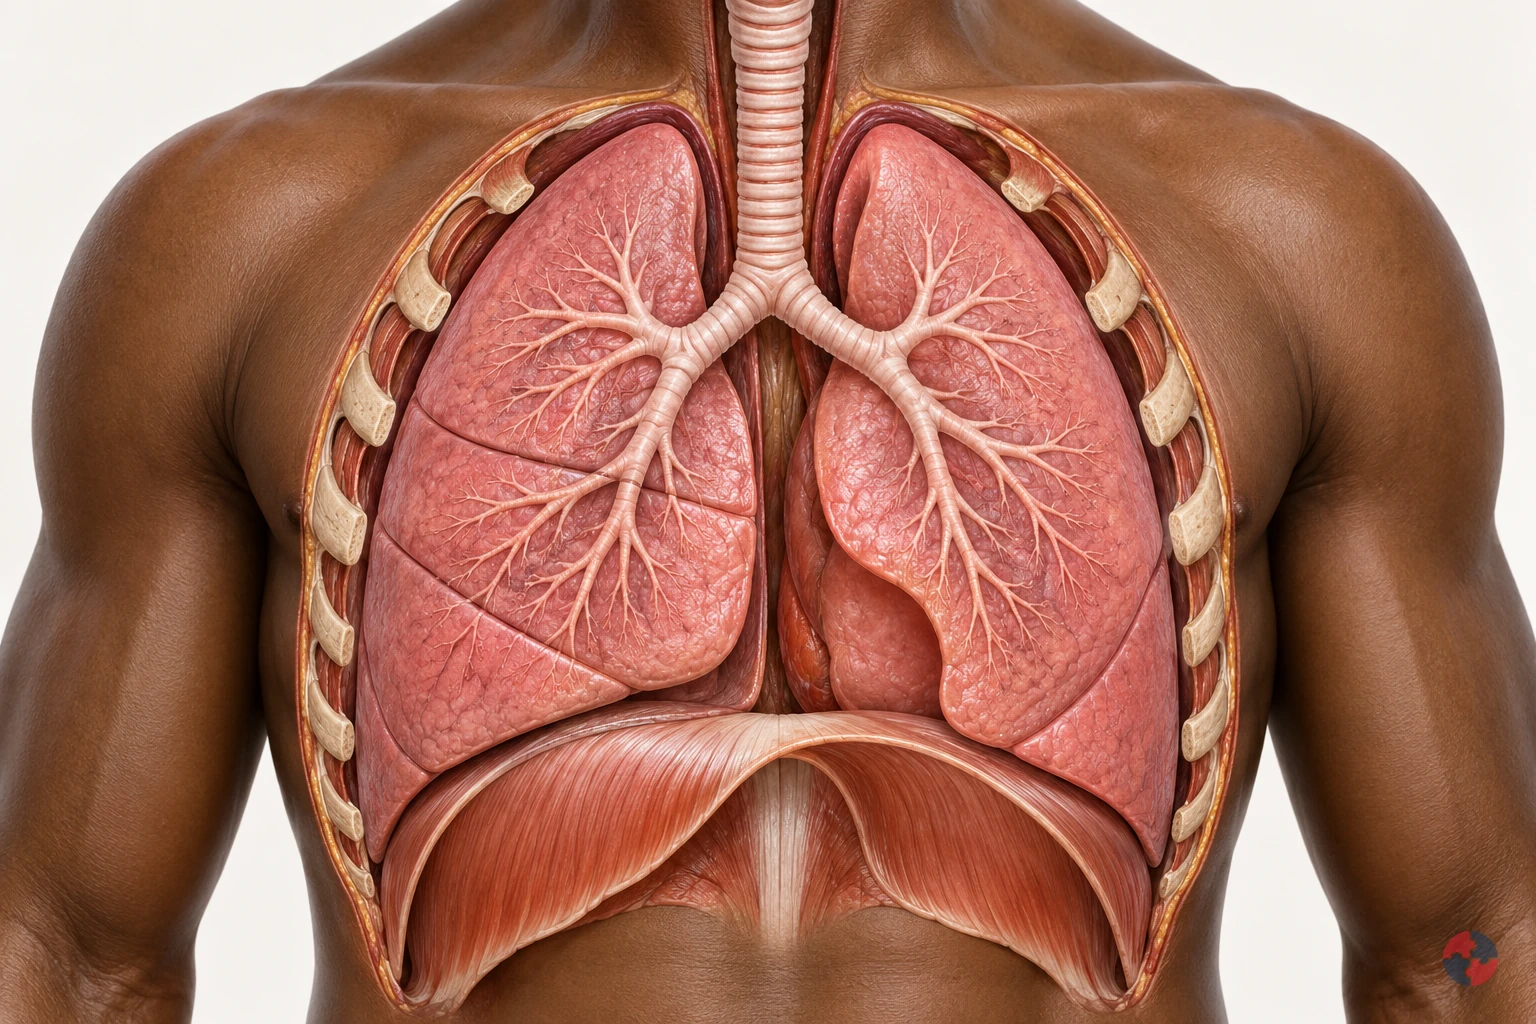
How do the lungs work, and how can workplace exposures affect breathing?
Interactive anatomy · Respiratory tract and lungs · Updated 2026-10-23
Read all anatomy and process explanations without the viewer
Simplified education, not diagnosis, a lung-function or oxygen-saturation test, an exposure calculator or a fitness-to-work assessment. No breath-holding challenge, breathing-rate score or personal health-data collection. Ordinary particle filters do not protect against every gas or oxygen deficiency. COPD and coal-dust topics may reuse normal anatomy only until separate mechanisms are reviewed.
Nose and mouth
Air enters and leaves here. The nose and mouth connect the outside air with the respiratory passages. Air moves through these openings on both the inward and outward breath. Follow the route towards the windpipe before looking at the smaller branches. The illustrated flow is air, a mixture of gases, rather than pure oxygen passing directly into blood. Frimley Health NHS Foundation Trust: How your lungs work · Central and North West London NHS Foundation Trust: How do we breathe?
Trachea
The windpipe carries air into the chest. The trachea, commonly called the windpipe, carries air down towards the chest. It divides into the two main bronchi that supply the lungs. Locate this shared passage before following either branch. Its role is to conduct air towards the gas-exchange regions and provide an outward route for the next exhalation. Frimley Health NHS Foundation Trust: How your lungs work
Bronchi
A main branch carries air into each lung. The two main bronchi take air from the windpipe into the right and left lungs. They divide into progressively smaller branches, distributing the breath through the lungs. Use the split as a landmark before following one highlighted route. These are air passages, distinct from the blood vessels that run through the same organs. Frimley Health NHS Foundation Trust: How your lungs work · University Hospitals of North Midlands NHS Trust: My lung surgery: about your lungs
Bronchioles
Smaller branches distribute air. Bronchioles are smaller branches of the airway system inside the lungs. Their branching routes lead towards clusters of alveoli, where the breath reaches the gas-exchange surface. Follow one branch to its end, using the others as context. This simplified route represents part of a much larger network supplying the lungs together. Frimley Health NHS Foundation Trust: How your lungs work
Alveoli
Tiny air sacs provide a gas-exchange surface. Alveoli are tiny air sacs at the ends of the small airway routes. Their close relationship with surrounding capillaries allows oxygen to pass towards blood and carbon dioxide towards alveolar air. Connect the highlighted cluster with the enlarged gas-exchange view. The enlargement changes the scale so the air space and neighbouring blood vessel can be distinguished. Frimley Health NHS Foundation Trust: How your lungs work · Central and North West London NHS Foundation Trust: How do we breathe?
Air–blood barrier
A thin boundary separates air from blood. The thin alveolar and capillary walls separate air in the sac from blood in its neighbouring vessel. Oxygen and carbon dioxide cross this boundary in opposite directions. Locate the tissue between the two spaces in the enlarged view. Blood cells remain in the vessel; the model does not represent an open connection through which air and blood mix. Central and North West London NHS Foundation Trust: How do we breathe?
Pulmonary capillaries
Small blood vessels pass beside the air sacs. Pulmonary capillaries are small blood vessels beside the alveoli. Blood moving through them receives oxygen and releases carbon dioxide across the thin exchange boundary, then continues through the circulation. Follow the labelled gas routes separately from the blood cells. These cells stay inside the capillary rather than moving into the air sac. Central and North West London NHS Foundation Trust: How do we breathe?
Diaphragm
This muscle helps make room for a breath. The diaphragm is a broad, dome-shaped breathing muscle beneath the lungs. It contracts and flattens downwards during inhalation, helping increase the space in the chest. During a quiet exhalation it relaxes towards its dome shape. Compare it with the rib cage: their changing positions help move air without the lung tissue acting as a contracting muscle. Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
Rib cage and breathing muscles
Chest movement changes the space around the lungs. The rib cage protects the chest organs and moves with the breathing muscles. Expansion upwards and outwards helps increase chest space during inhalation; relaxation reduces that space during a quiet exhalation. Compare this movement with the diaphragm below the lungs. Together these structures provide the mechanics that allow air to move through the airways. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
Pleura
Two thin layers surround the lungs and line the chest. The pleura has two thin layers around the lungs and inside the chest wall. A small amount of fluid between them allows the surfaces to slide with less friction as breathing changes the chest space. Locate this outer covering separately from the internal air sacs; it is not the thin air–blood exchange boundary. Blackpool Teaching Hospitals NHS Foundation Trust: Pleural clinic
Open the complete process transcript
The process, step by step
1 · Make space
Breathing in begins with a change in the space inside the chest. The diaphragm, a dome-shaped muscle beneath the lungs, contracts and moves downwards. Muscles around the ribs help lift the chest upwards and outwards. As the lungs expand with this changing space, air can enter through the airways. Locate the diaphragm and rib cage together rather than treating the lungs as muscles that pull themselves open. The model separates the movement into a teaching step so you can follow its purpose. In the body, chest movement, airflow and blood circulation are connected parts of a continuing process. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
What to watch: Locate the diaphragm beneath the lungs and the rib cage around them; compare their positions with the space occupied by the lungs.
Why it matters: Changing the chest space draws air into the lung passages. The breathing muscles supply the movement, while the lungs expand with the chest to receive the next breath.
Explore this step: Select the diaphragm and rib cage in turn, then explain how their movement helps air enter without the lungs contracting like muscles.
2 · Move air
Air entering through the nose or mouth travels down the trachea, or windpipe, towards the chest. The trachea divides into the two main bronchi, with one route supplying each lung. Follow this continuous passage in the whole-chest view before moving into the smaller branches. The moving air is a mixture of gases, including oxygen; it is not a stream of pure oxygen travelling straight into the blood. These larger airways carry the breath towards the places where gas exchange happens. The same connected passages also provide the outward route when air is breathed out. Frimley Health NHS Foundation Trust: How your lungs work
What to watch: Start at the nose and mouth, follow the trachea downwards and find the split into the right and left main bronchi.
Why it matters: The larger passages distribute air to both lungs and connect the outside air with the smaller branches inside. Gas exchange takes place further along the route, rather than within the windpipe.
Explore this step: Trace the route to each lung and distinguish the tubes carrying air from the separate vessels carrying blood.
3 · Reach the air sacs
Inside each lung, the bronchi divide into smaller branches called bronchioles. These passages distribute air towards clusters of tiny air sacs, the alveoli. Follow one branch in the close-up and connect its end with an air-sac cluster, using the other branches as surrounding context. These routes distribute the breath throughout the lungs rather than supplying only one working air sac. A real lung contains many branching routes and air sacs operating together. This distribution brings air close to a large network of small blood vessels, preparing for the exchange shown in the next view. Frimley Health NHS Foundation Trust: How your lungs work
What to watch: Follow one smaller airway to the cluster of air sacs at its end, keeping the other branches as surrounding context.
Why it matters: Branching delivers air throughout the lungs instead of to one large chamber. The many air sacs bring the inhaled gases close to blood vessels where oxygen and carbon dioxide can cross.
Explore this step: Trace one complete branch to its air sacs, then explain how the many branches distribute air throughout the lungs.
4 · Change scale
The lesson now changes from a branching airway to an enlarged air–blood interface. An alveolus contains air; beside it runs a capillary containing blood. Their very thin walls form the boundary across which gases can move. Locate the air space, the separating tissue and the inside of the vessel before following any gas symbols. The magnified view represents a tiny part of the same lung, not a separate organ or a hole that joins air and blood into one space. The enlargement helps explain how the two systems can exchange gases while keeping their contents separate. Central and North West London NHS Foundation Trust: How do we breathe?
What to watch: Find the air inside the enlarged alveolus, the thin separating boundary and the neighbouring capillary with blood cells inside it.
Why it matters: A close boundary allows gases to cross between alveolar air and capillary blood. Keeping the two spaces separate lets ventilation and circulation cooperate without blood cells entering the air sac.
Explore this step: Identify the air space and blood-vessel space, then point to the boundary each gas must cross between them.
5 · Exchange gases
At the air–blood boundary, oxygen moves from the alveolar air into the capillary blood. At the same time, carbon dioxide carried back from the body moves from the blood into the air sac. The two gases cross in opposite directions; blood cells stay within the vessel. Follow each labelled symbol separately so that exchanging gases is not confused with mixing the air and blood together. Blood then carries oxygen onwards towards the heart and the body’s tissues. The teaching symbols simplify continuous gas movement, and their size, colour and speed do not represent a measurement. Central and North West London NHS Foundation Trust: How do we breathe?
What to watch: Follow the O₂ symbol towards the capillary and the CO₂ symbol towards the air sac, while locating the blood cells within the vessel.
Why it matters: Oxygen can be carried onwards for use by the body, while carbon dioxide returns to the airways for removal. Both transfers connect the breath with the continuing circulation of blood.
Explore this step: Trace the two gas routes in opposite directions and explain why a blood cell should remain inside the capillary.
6 · Breathe out
During a quiet breath out, the diaphragm and other breathing muscles relax. The diaphragm returns towards its dome shape, chest space decreases and air moves back along the airways to the nose or mouth. This outgoing air carries carbon dioxide that crossed from the blood into the alveoli. Trace the route in reverse without reversing the direction of blood circulation: oxygen-carrying blood continues towards the heart while another breath prepares to enter. The model presents a single cycle to explain the relationship. It does not show breathing as a series of separate events in which circulation stops between steps. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
What to watch: Compare the diaphragm and chest with the inhalation step, then follow the outward airway route from the lungs to the nose or mouth.
Why it matters: Exhalation removes air containing carbon dioxide from gas exchange. Meanwhile, blood circulation continues carrying oxygen onwards, linking this breathing cycle with the needs of the rest of the body.
Explore this step: Trace the outward air route and the onward blood route separately, then describe why they are connected processes with different pathways.
Mechanisms and their limits
Sensitiser-related asthma Some people become sensitised to workplace substances such as flour or wood dust. Later exposure may trigger inflamed, narrowed airways, sometimes at low levels. Compare the airway opening, not the size of the whole lung. Sensitisation and later triggering are different phases, shown without a fixed clock. Work can also worsen existing asthma. Not all work-related asthma is an allergic reaction. A symptom pattern can prompt investigation but cannot establish a diagnosis from this model. HSE: Asthma: an overview · NHS: Asthma · HSE: Flour dust and risks to bakers
Assess sensitisers and maintain exposure controls
Get clinical advice about asthma symptoms
Sensitiser-related asthma — follow the anatomy
Look at: The airway opening, its muscle and swollen lining.
What changes: In asthma, narrowing, swelling and mucus can restrict the route for air.
Why it matters: Breathing may become difficult, with wheeze, cough or chest tightness.
What to do: Prevent exposure to the cause and report breathing symptoms for medical assessment.
Flour handling and later occupational asthma
Bakery: flour is tipped and benches are dusted repeatedly during production. Time jump: sensitisation may develop over a variable period; a later exposure may trigger symptoms. This is not asthma developing in 32 seconds. Not every exposed or sensitised person develops asthma. Wheeze or timing alone does not establish the cause or diagnosis.
A dusty bakery task Flour is tipped into a mixer and used to dust the bench. Review low-dust ingredients and careful handling before relying on the worker to avoid a visible cloud. HSE: Flour dust and risks to bakers
Repeated exposure, then a time jump Breathing flour dust can lead to sensitisation in some people over time. The timeline now jumps to a later contact after a hypersensitive state has developed in this chosen example. HSE: Asthma: an overview · HSE: Flour dust and risks to bakers
A later contact can narrow airways The airway wall becomes inflamed and the breathing passage narrows in the illustrative asthma episode. Symptoms may occur during the task or later; this is not the same as identifying asthma by a short animation. HSE: Asthma: an overview · NHS: Asthma
Report patterns and reduce exposure Report work-related breathing problems promptly and obtain clinical advice. Review low-dust flour, transfer/handling and the full control assessment; use the emergency panel immediately for severe breathing difficulty. HSE: Advice for employers: occupational asthma · HSE: Flour dust and risks to bakers · NHS: Shortness of breath
Read the practice situations and all answer explanations
LU-Q1: Which plan best addresses the hazard?
A team plans repeated concrete cuts with a handheld cut-off saw. Dust can enter the operator’s and nearby workers’ breathing zones.
Open a window and use the same dry-cutting method. — A window alone does not control dust generated beside the face. Choose task controls that prevent or capture it at source.
First reduce the need to cut, then assess source suppression or extraction and any required suitable RPE. — This addresses the task before exposure occurs. Check that suppression or extraction works and that required RPE is suitable, fitted and used.
Continue while nobody is coughing. — Symptoms are not an exposure monitor. Harmful respirable dust may be invisible, and a worker can feel well during exposure.
HSE: Construction dust: cutting paving blocks, kerbs and flagsLU-Q2: What is the most useful next action?
A bakery worker notices repeated wheeze after dusty flour tasks, including some symptoms later in the evening.
Report the pattern and seek medical and workplace assessment. — Reporting the pattern allows exposure controls and clinical assessment to be reviewed. Symptoms can be delayed; a clinician may need further investigation.
Use this model to diagnose occupational asthma. — The model explains a mechanism. It cannot diagnose asthma or establish that work caused it.
Assume the task is safe if breathing improves away from work. — Improvement away from work may be useful information for investigation, but it does not show that returning to the same exposure is safe.
HSE: Asthma: an overview · HSE: Advice for employers: occupational asthma · NHS: Asthma · HSE: Flour dust and risks to bakersLU-Q3: What is the important distinction?
One diagram shows a narrowed airway at LUN03–04. A second shows scarred gas-exchange tissue around LUN05–07.
They show the same disease at successive stages. — Narrowed airways and scarred lung tissue are different changes. One is not automatically the next stage of the other.
Both effects disappear when airborne dust settles. — Removing airborne dust does not reverse established fibrosis. Controlling further exposure remains important.
Airway narrowing and tissue fibrosis are different mechanisms. — Correct. Airway narrowing affects the passage for air; fibrosis affects lung tissue and its function. Neither picture supplies an individual diagnosis.
NHS: Silicosis · NHS: AsthmaSources and how the model is made
The opening images are AI-generated anatomical illustrations. The interactive 3D models and labelled SVG diagrams use original procedural artwork. These teaching images are not medical scans or diagnostic tools. Source references support the learner explanations and do not grant artwork rights.
- Frimley Health NHS Foundation Trust: How your lungs work — Normal airway branching, air sacs and capillary gas exchange; factual text only.
- Central and North West London NHS Foundation Trust: How do we breathe? — Thin alveolar/capillary walls, opposing gas transfer, circulation and chest mechanics. No illustrations or exercises copied.
- Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved — Diaphragm movement and breathing-muscle context only; this module does not prescribe breathing exercises.
- HSE: Health risks from welding — Welding-related airway irritation, possible deeper injury and irritant asthma; not a universal pattern for every gas.
- HSE: Asthma: an overview — Sensitisation, later triggering and work aggravation. Legacy labelling language and statistics are not reused.
- HSE: Advice for employers: occupational asthma — Exposure prevention, controls and health surveillance only; legacy legislation wording is not reused.
- NHS: Silicosis — Silica-associated inflammation/fibrosis, varying latency, irreversible damage and possible progression after exposure stops.
- HSE: Why is asbestos dangerous? — Asbestosis, mesothelioma and pleural disease are distinct; long disease latency.
- HSE: Construction dust: cutting paving blocks, kerbs and flags — Task design, source suppression/extraction, suitable RPE and checking controls; not a generic dust safe-dose rule.
- NHS: Shortness of breath — Emergency recognition of severe breathing difficulty and 999; emergency advice is outside the activity.
- NHS: Asthma — Narrowed/swollen airways, symptoms and clinical diagnosis; no medication doses or treatment plan reproduced.
- University Hospitals of North Midlands NHS Trust: My lung surgery: about your lungs — Right/left lung lobe counts and airway anatomy; no source image copied.
- Blackpool Teaching Hospitals NHS Foundation Trust: Pleural clinic — Pleural layers and the small lubricating fluid layer outside lung tissue; no procedural teaching included.
- HSE: Asphyxiation hazards in welding and allied processes — Oxygen-deficient spaces and need for independent air supply; no unprotected entry or rescue.
- HSE: Respiratory protective equipment at work — RPE selection must match the contaminant and conditions; filtering protection is not a supply of oxygen.
- HSE: Flour dust and risks to bakers — Flour sensitisation and practical reduction of dusty handling; exposure-limit numbers are not reused.
- Health and Safety Executive: Asbestos essentials — Task planning, training and competent asbestos work arrangements for the maintenance exposure example; not permission to disturb unknown material or a licence/classification decision.
- Health and Safety Executive: Welding fume: protect your workers — Alternative joining, fume reduction, LEV, suitable RPE and maintained controls for the welding-fume example. No unprotected exposure or rescue procedure.
What symptoms should trigger action?
Symptoms should be treated as a possible control failure until competent review says otherwise.
Wheeze, chest tightness, breathlessness, cough or a work-related pattern need prompt reporting and clinical or occupational-health assessment. Remove the worker from further exposure pending competent advice and investigate controls. HSE - Isocyanates in construction.
- Chest tightness — Possible asthma symptom. Report, record exposure and refer to OH/medical route.
- Wheeze or breathlessness — Could indicate respiratory sensitisation. Remove from exposure pending advice.
- Persistent cough — May be work-related respiratory sign. Review exposure tasks and surveillance.
- Flu-like shivers after spraying — HSE flags this as a possible early sign. Investigate controls and health route.
- Symptoms worse after work or at night — Work pattern may be missed during shift. Ask timing questions in surveillance.
- Skin rash/dermatitis — Skin sensitisation or irritant exposure possible. Review gloves, hygiene and skin surveillance.
Why is spraying especially high risk?
Spraying breaks liquid product into fine droplets that can travel, remain airborne and be inhaled.
HSE guidance highlights that spraying can produce very high exposure because mist droplets are easily breathed in and because more product is used in a short time. Conventional spraying, HVLP and airless systems all have different overspray and injection hazards, so the equipment choice matters. See HSG276 - Isocyanate paint spraying; INDG388 - Safety in isocyanate paint spraying.
The spray area must be managed as a contaminated atmosphere until it is clear. A worker who lifts an air-fed visor to inspect finish immediately after spraying can inhale mist despite having worn BA during the spraying pass.
- Mist leakage — Can expose bystanders outside booth/room. Maintain enclosure and extraction.
- Clearance time unknown — Workers may remove BA too soon. Measure and display clearance time.
- Visor lifted — High exposure can occur after spraying. Keep BA on until outside clear area.
- Spray gun cleaning — Exposure can occur during wash-out. Use controlled cleaning and RPE.
- Outdoor spraying — Wind can carry mist. Plan exclusion, wind direction and controls.
- Airless injection hazard — High pressure can inject paint into skin. Guard tips, pressure control and training.
How should COSHH assessment be carried out?
A suitable COSHH assessment must identify the product, task, route, exposure group and control reliability.
A weak assessment says 'wear mask'. A strong assessment identifies the isocyanate type, product use, spray method, booth or room condition, clearance time, RPE specification, breathing-air quality, bystander exposure, skin contact, cleaning work, maintenance and biological monitoring plan. See COSHH Regulations 2002; COSHH Regulations (Northern Ireland) 2003.
Assessment must include foreseeable poor practice: rushing, lifting visors, cleaning guns, spraying small jobs outside a booth, allowing others into the area too early and failing to maintain air supply.
- Which isocyanate product is used? — MDI, TDI, HDI/IPDI risks and monitoring differ. SDS and product register.
- Is it sprayed, brushed, mixed or heated? — Aerosol generation changes exposure. Task observation.
- Where does mist go? — Bystanders and leakage may be exposed. Booth smoke test and clearance measurement.
- What RPE is specified? — For isocyanate paint spraying, filtering respirators are unsuitable; suitable air-fed breathing apparatus is required. Assess other isocyanate processes for their actual task. RPE assessment and maintenance record.
- How is control verified? — Controls can fail silently. Biological monitoring and surveillance.
- What symptoms have been reported? — Health reports may show failure. Confidential reporting and OH referral.
How should isocyanate exposure be controlled?
Controls should eliminate or minimise aerosol and skin exposure before relying on behaviour.
Start with product and task assessment. Remove isocyanate spraying where feasible; otherwise combine verified booth extraction and clearance with protected spraying and exposure checks. The hierarchy table distinguishes engineering control from air-fed RPE. HSG276 - Isocyanate paint spraying.
In a two-pack vehicle-paint job, the first choice is whether the finish can be achieved without isocyanate spray. If spraying remains necessary, the technical lead confirms the product and booth specification; the sprayer checks extraction and air supply before entry, keeps others out during the measured mist-clearance period and uses the specified air-fed protection. A failed booth test, unknown product or symptom report stops the task and triggers exposure review. HSE HSG276 explains the spray-booth control approach.
| Control priority | Practical control | Example |
|---|---|---|
| Eliminate | Avoid isocyanate product or spraying where possible. | Use non-isocyanate alternative or prefinished component. |
| Substitute | Replace the product or process with an assessed less hazardous alternative where feasible. Quantity reduction is minimisation, and improved spray equipment is engineering/process control; neither is automatically substitution. | A genuinely lower-hazard replacement needs assessment. HVLP can improve transfer efficiency but residual isocyanate mist remains and required spray protection still applies. |
| Engineering | Enclose or separate the task and capture aerosol or fume at source. | Verify booth or local exhaust ventilation, access control and bystander separation. |
| Administrative | Brief, supervise and stop unsafe practices. | No visor lifting, no uncontrolled cleaning. |
| Personal protection | Use suitable gloves, coveralls, eye protection and BA. | RPE programme and skin protection. |
What should be controlled around RPE, air-fed BA and spray booths?
RPE is a life-critical control in isocyanate spraying and must be treated as a programme, not a mask purchase.
For isocyanate paint spraying, ordinary filtering respirators are unsuitable. Select suitable air-fed breathing apparatus to the HSE task guidance, with assigned protection factor at least 20 and a low-flow indicator. A half-mask air-fed device in a spray room needs clear, continuing biological-monitoring evidence that exposure is adequately controlled; it is not the default choice. Verify manufacturer minimum flow, clean breathing-air quality, supply integrity and booth clearance before spraying and at use. HSG276 - Isocyanate paint spraying; HSG53 - Respiratory protective equipment at work. HSE paint-spraying RPE guidance
Tear-off visor covers, lighting, low-flow indicators, air-line checks and supervisor observation all matter because poor visibility or low air flow can tempt workers into unsafe behaviour.
| Control | Good practice | Evidence |
|---|---|---|
| Air-fed BA | Suitable air-fed BA, APF at least 20, low-flow indicator; half-mask only with continuing biological-monitoring evidence. | Selection record, manufacturer minimum-flow and air-supply checks, low-flow test and monitoring review. |
| Breathing air quality | Clean air at required pressure/flow. | Air quality test and compressor maintenance. |
| Booth clearance time | Measured and communicated. | Clearance test and sign. |
| Extraction | Maintained and not leaking mist. | LEV/booth maintenance record. |
| Visor discipline | BA kept on until outside/clear. | Observation and training. |
| Fit testing | For tight-fitting RPE where used. | Fit-test record. |
How does biological monitoring help?
Biological monitoring checks whether exposure control is working in real people doing real tasks.
HSE explains that urine biological monitoring can be used to check isocyanate exposure, especially where air-fed BA is relied on. This is valuable because booth, RPE and work-practice controls can all look acceptable but still fail in practice. See HSE - Biological monitoring and paint spraying.
Results should be interpreted by competent people and used to improve controls. Biological monitoring is not a blame tool; it is a reality check on the system.
| Element | Why it matters | Evidence |
|---|---|---|
| Sampling timing | Select analysis for the isocyanates actually used and sample representative work at the end of potential exposure, within about an hour, following laboratory instructions. | Sampling instruction and chain of custody. |
| Worker briefing | Workers understand purpose and privacy. | Consent and information record. |
| Result interpretation | Competent review turns result into action. | OH/hygiene report. |
| Control review | Unexpected result triggers booth/RPE/work-practice review. | Action tracker. |
| Trend review | Shows whether programme is improving control. | Monitoring dashboard. |
Programme: plan, sample, interpret, correct, verify
Use a laboratory/competent adviser to select analysis for the actual isocyanates, sample representative work at the end of potential exposure within about an hour, and document product, task, sampling time and RPE/work conditions. Interpret results competently, investigate controls where exposure is indicated and repeat testing after corrective action when indicated. HSE recommends annual monitoring for vehicle spray painters; frequency for other work follows its assessment.
An exposure test does not diagnose asthma or clear a symptomatic worker to remain exposed. Normal urine results do not override symptoms, and staying below a WEL alone does not adequately control every sensitiser risk. Biological monitoring, airborne measurement and clinical health surveillance answer different questions.
What health surveillance is needed?
Health surveillance helps detect early signs of occupational asthma and dermatitis.
HSE guidance for isocyanate-exposed workers highlights respiratory health surveillance, including lung function testing and questionnaires, and skin surveillance where dermatitis risk exists. Surveillance should start early for new workers and continue periodically. See HSE - Health surveillance in motor vehicle repair.
Health surveillance does not replace exposure control. If surveillance finds symptoms, the correct response is to protect the worker and investigate exposure, not simply repeat the test later.
| Surveillance element | Purpose | Evidence |
|---|---|---|
| Baseline questionnaire | Records starting respiratory/skin status. | OH health record. |
| Early follow-up | Detects early sensitisation pattern. | 6-week/6-month style review where applicable. |
| Annual review | Ongoing detection and trend. | Lung function and questionnaire record. |
| Skin checks | Identify dermatitis or sensitisation. | Skin surveillance record. |
| Referral route | Escalates symptoms quickly. | OH referral and exposure review. |
How does isocyanate asthma appear in real workplaces?
Worked scenarios help supervisors recognise exposure failure before permanent disease develops.
Compare the spray setup, bystander entry and symptom report in each scenario. The decision is whether exposure prevention is working now, who can hold the task, and what evidence permits restart.
- Panel beater does a small 2K spray outside booth — Shortcut exposes worker and nearby team. Use booth/controlled area or alternative product/method.
- Sprayer lifts visor to inspect finish — Mist still present during clearance time. Keep BA on until outside/clear and improve visor visibility.
- Contractor sprays coating in a corridor — Mist drifts through occupied building. Plan enclosure, exclusion, ventilation and communication.
- Biological monitoring result high — Controls not working despite paperwork. Review booth, BA, work practice and retrain.
- Worker reports wheeze at night — Delayed symptom pattern may be missed. Remove from exposure pending OH/medical advice and investigate.
How should a 2K spray-painting job be controlled from start to finish?
A detailed bodyshop example shows how exposure control depends on every stage, not only the few minutes of spraying.
Consider a vehicle repair task where a panel beater prepares a repaired door and wing, mixes a 2K coating, sprays primer and topcoat, allows the finish to cure, cleans the gun and then polishes the job. The isocyanate risk is not limited to the spray trigger being pulled. Exposure can occur during mixing, spraying, mist clearance, visor lifting, cleaning, handling contaminated surfaces and allowing other workers into the booth too early. See HSG276 - Isocyanate paint spraying.
The control plan should therefore cover the whole job sequence. The product should be identified from the safety data sheet, the booth should be checked before work, the air-fed breathing apparatus should be checked and worn correctly, the clearance time should be known, biological monitoring should be timed so it reflects real exposure, and health surveillance should ask about delayed symptoms such as night-time wheeze or chest tightness after spraying days.
- Product selection and mixing — Confirm 2K/isocyanate content, use controlled mixing, gloves, eye protection and ventilation. Decanting into unlabelled pots, poor gloves, splashes or assuming mixing is low risk.
- Booth preparation — Check extraction, lighting, doors, manometer/airflow indicators, housekeeping and no unauthorised persons. Spraying in a dirty booth, poor airflow, blocked filters or doors opened during spraying.
- Air-fed BA preparation — Check air supply, low-flow warning, hose condition, visor clarity, compressor location and breathing-air quality records. Low air flow, contaminated air, damaged hose or visor covers not used so the wearer lifts the visor.
- Spraying — Keep BA on, maintain spray technique, avoid unnecessary overspray and exclude bystanders. Spraying outside the booth or using a shortcut for a small repair.
- Curing and clearance — Treat the booth/room as contaminated until measured clearance time has passed. Worker lifts visor or another person enters to inspect the finish too soon.
- Cleaning spray gun — Use controlled cleaning methods and RPE where aerosol or solvent/isocyanate exposure may occur. Gun is cleaned by spraying solvent or product without proper RPE.
- Biological monitoring — Collect samples at the correct time and interpret results through competent occupational hygiene/OH routes. Test is missed, taken at the wrong time or treated as a worker blame exercise.
- Health surveillance — Use respiratory questionnaires, lung function checks and early referral for symptoms. Night-time cough/wheeze is dismissed as a cold or smoking-related without exposure review.
- Symptom escalation — Remove from exposure pending competent advice and investigate the control system. Worker continues spraying to finish the job while symptoms worsen.
- Learning and assurance — Review booth records, BA checks, behaviour observations and monitoring trends. Management only keeps training certificates and assumes the system is working.
Two-pack spray paint repair in a bodyshop
Task, material and setting: A painter prepares a vehicle panel for two-pack isocyanate paint in an enclosed spray booth; a neighbouring worker may enter during booth clearance.
People and prerequisites: The supervisor confirms product identity and safety data, spray method, booth flow/clearance time, air supply, sprayer competence and bystander exclusion.
Before: Before spraying, consider an isocyanate-free coating or non-spray method if the specification permits; otherwise verify booth extraction, air-fed respiratory protection and the task COSHH assessment.
During: During spraying and mist clearance, keep the air-fed protection on and the booth access controlled; do not lift the visor in the mist.
Hold or stop: Stop if booth flow or supplied air fails, the product is unknown, a bystander enters, the visor is lifted in mist or symptoms are reported.
Completion and hand back: A competent manager checks the fault and exposure pathway, arranges health advice for the worker, and restarts only after controls and clearance arrangements are verified.
Evidence: Keep product/SDS, substitution decision, booth test and clearance evidence, RPE/air-supply checks, biological-monitoring review, confidential health route and restart record.
What records prove isocyanate asthma risk is managed?
Records should show assessment, control, monitoring, health surveillance and action.
Records should prove that controls were selected, implemented, checked and improved. The table helps distinguish useful evidence from records that exist only because someone expected a document.
- Product register/SDS — Identifies isocyanate products. Is it current after procurement changes?
- COSHH assessment — Links task to controls and surveillance. Does it cover cleaning and bystanders?
- Booth/LEV maintenance — Shows extraction remains effective. Are defects closed?
- RPE records — Shows BA, air quality and checks. Are users trained and supervised?
- Biological monitoring — Checks real exposure control. Are results acted on?
- Health surveillance — Detects early symptoms. Are referrals followed up confidentially?
Which legal duties apply to isocyanate asthma?
A two-pack paint task falls under the hazardous-substance route for the work location: Great Britain’s COSHH 2002 or Northern Ireland’s COSHH guidance and 2003 regulations. The assessment must address the product, spray mist, skin contact, bystanders, extraction and health effects. HSE HSG276 is task guidance for spray booths; it is not a replacement for either jurisdiction’s law.
A symptom report triggers prompt exposure review and suitable clinical referral, while any statutory occupational-disease report is a separate decision under the relevant GB or NI reporting rules. The supervisor should preserve the product identity, booth and air-supply checks, clearance-time evidence and the worker’s exposure history without putting private health details into a general team log.
| Jurisdiction | Duty route | Practical decision and evidence |
|---|---|---|
| Great Britain | COSHH Regulations 2002 | Assess the actual isocyanate product and task; prevent or adequately control exposure, maintain controls and use health surveillance where required. Official text and guidance: COSHH Regulations 2002; HSG276 - Isocyanate paint spraying |
| Northern Ireland | COSHH Regulations (Northern Ireland) 2003 | Apply the distinct NI hazardous-substances regime and HSENI guidance to spraying, foaming and other exposure routes. Official text and guidance: COSHH Regulations (Northern Ireland) 2003; HSENI COSHH guidance |
| Great Britain | Work-related asthma reporting under GB RIDDOR, where criteria are met | Assess reportability after a medical diagnosis and work link; do not treat a symptom alone as a confirmed statutory case. Official text and guidance: GB RIDDOR reporting guidance |
| Northern Ireland | Reportable occupational disease under the NI reporting regime, where criteria are met | Use the HSENI disease-reporting route after competent diagnosis and a work link; investigate control failure without waiting for a report. HSENI reporting route: HSENI disease reporting. |
How could BuildOut Ltd manage this in practice?

BuildOut Ltd would manage isocyanate asthma through product control, COSHH assessment, exclusion, RPE, monitoring and health surveillance.
BuildOut Ltd is a contractor with maintenance workshops, coating works and occasional spray tasks. It needs to prevent small jobs and contractor work from bypassing the controls used in formal spray operations.
- Assessing — BuildOut identifies all isocyanate products, spray tasks, bystander exposures and cleaning activities. COSHH register and task inventory.
- Implementing — Spraying is restricted to controlled areas with air-fed BA, clearance rules and exclusion zones. Method statement and booth checks.
- Monitoring — Biological monitoring checks whether controls are working in real work. Urine monitoring programme and action log.
- Health surveillance — Respiratory and skin surveillance is provided for exposed workers. OH scheme and health records.
- Training — Workers learn symptoms, visor discipline, clearance time, RPE use and reporting. Training and supervisor observation.
- Improving — Any symptom report or high monitoring result triggers control review and management action. RCA and action tracker.
How can the hierarchy of controls reduce risks while spraying a vehicle with isocyanate-containing paint?
For two-pack vehicle spraying, first test whether the coating or application method can avoid isocyanate aerosol. Where spraying remains, verify booth extraction, clearance and suitable air-fed respiratory protection; stop for failed controls or symptoms.
| Control priority | Task-specific control and feasibility | Owner, verification, failure and stop point |
|---|---|---|
| Elimination | Check whether a non-isocyanate coating or factory-finished panel meets the customer and product specification so no isocyanate spray is needed. | Owner: purchasing and technical lead. Trial finish and durability; stop if substitute performance or ingredient identity is unverified. HSE task guidance |
| Substitution | Where coating change is possible, test a non-spray brush/roller application or lower-aerosol system using product data; a different two-pack product is not automatically safer. | Owner: competent COSHH assessor. Compare safety data, application and exposure; hold a change that creates uncontrolled solvent or skin risk. HSE task guidance |
| Engineering | Use an enclosed spray booth with appropriate extraction, defined mist-clearance time, filtered air supply and controlled access. Commission airflow, verify clearance, check pressure/filters and exclude bystanders. | Owner: booth engineer and supervisor. Keep test and maintenance evidence; stop for failed extraction, unclear clearance or open access. HSE task guidance |
| Administrative | Use a task COSHH assessment, product identity check, authorised sprayer, cleaning method and observed clearance rule. Biological monitoring and health surveillance check failure; they do not replace exposure prevention. | Owner: supervisor and occupational health. Review results and worker reports; hold spraying after a high result or symptoms until the cause is investigated. HSE task guidance |
| Personal protection | For isocyanate spray mist, select and maintain suitable air-fed respiratory protective equipment and compatible gloves/coveralls. Verify clean air supply, breathing equipment and donning before entry; keep protection on through clearance. | Owner: RPE programme lead and sprayer. Check defects and air supply each task; stop for failed supply, poor fit, damaged equipment or visor lifted in mist. HSE task guidance |
How can the ERICPD hierarchy of controls reduce risks while spraying a vehicle with isocyanate-containing paint?

| Control level | Control for this activity | Owner and verification | Stop / restart decision |
|---|---|---|---|
| Eliminate | Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits. | Task owner verifies that the proposed change removes the named hazardous step, including foreseeable cleaning, maintenance and work transferred elsewhere. | If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls. |
| Reduce, including substitution | Validate a suitable isocyanate-free coating or non-spray process, checking performance and other hazards. | Competent task/process owner validates suitability, compatibility and new hazards against the actual operating requirements before the alternative is adopted. | Reject an alternative if its performance is unproved or its new hazards are unresolved. |
| Isolate | Restrict the spray area and prevent other workers entering during spraying and the verified clearance period. | Supervisor checks the actual boundary, affected people and connected work; verify separation or isolation before allowing access. | Hold or stop for failed booth or breathing air, unknown paint, premature entry or unresolved exposure-control failure. |
| Control: physical safeguards | Use a suitable maintained spray booth/room with effective extraction; verify containment and the measured clearance arrangement. | Competent equipment/process owner checks paint identity, booth function, clearance period, breathing-air supply and required exposure checks. | Hold or stop for failed booth or breathing air, unknown paint, premature entry or unresolved exposure-control failure. |
| Control: work method and response | Follow the approved spraying and exit/entry procedure, keep required training current and arrange appropriate exposure monitoring and health surveillance. | Supervisor confirms the work limits, competent cover, communication and stop/restart authority with the people doing this activity. | Hold work when the agreed limits, competent cover or effective communication cannot be maintained. |
| PPE | Use suitable air-fed breathing apparatus for isocyanate spraying and during the required clearance period, plus compatible skin and eye protection; do not lift the visor early. | Assessor confirms whether personal protection is needed and checks suitability, condition, compatibility and any required fit evidence. | Do not use unsuitable protection or rely on PPE to continue after an essential source control fails. |
| Discipline | Check booth, air supply and protective equipment, act on failed monitoring and review product or process changes before reuse. | Release only after bodyshop owner verifies the restored booth, air-fed protection and approved work method. Retain verification and unresolved restrictions at handover. | Keep the task on hold until required reinstatement evidence and unresolved defects are accepted by the responsible owner. |
How can the ISO 45001 hierarchy of controls reduce risks while spraying a vehicle with isocyanate-containing paint?

| Control level | Control for this activity | Owner and verification | Stop / restart decision |
|---|---|---|---|
| Elimination | Use suitable prefinished parts or remove unnecessary spray refinishing where the job permits. | Task owner verifies that the proposed change removes the named hazardous step, including foreseeable cleaning, maintenance and work transferred elsewhere. | If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls. |
| Substitution | Validate a suitable isocyanate-free coating or non-spray process, checking performance and other hazards. | Competent task/process owner validates suitability, compatibility and new hazards against the actual operating requirements before the alternative is adopted. | Reject an alternative if its performance is unproved or its new hazards are unresolved. |
| Engineering controls | Restrict the spray area and prevent other workers entering during spraying and the verified clearance period. | Supervisor checks the actual boundary, affected people and connected work; verify separation or isolation before allowing access. | Hold or stop for failed booth or breathing air, unknown paint, premature entry or unresolved exposure-control failure. |
| Engineering controls | Use a suitable maintained spray booth/room with effective extraction; verify containment and the measured clearance arrangement. | Competent equipment/process owner checks paint identity, booth function, clearance period, breathing-air supply and required exposure checks. | Hold or stop for failed booth or breathing air, unknown paint, premature entry or unresolved exposure-control failure. |
| Administrative controls | Follow the approved spraying and exit/entry procedure, keep required training current and arrange appropriate exposure monitoring and health surveillance. | Supervisor confirms the work limits, competent cover, communication and stop/restart authority with the people doing this activity. | Hold work when the agreed limits, competent cover or effective communication cannot be maintained. |
| PPE | Use suitable air-fed breathing apparatus for isocyanate spraying and during the required clearance period, plus compatible skin and eye protection; do not lift the visor early. | Assessor confirms whether personal protection is needed and checks suitability, condition, compatibility and any required fit evidence. | Do not use unsuitable protection or rely on PPE to continue after an essential source control fails. |
| Administrative controls | Check booth, air supply and protective equipment, act on failed monitoring and review product or process changes before reuse. | Release only after bodyshop owner verifies the restored booth, air-fed protection and approved work method. Retain verification and unresolved restrictions at handover. | Keep the task on hold until required reinstatement evidence and unresolved defects are accepted by the responsible owner. |
What training supports isocyanate asthma prevention?
A sprayer’s competence must be observed across product selection, booth operation, respiratory protection, cleaning and symptom response, not inferred from course attendance.
Sprayers must demonstrate product checks, booth and air supply checks, correct air-fed respiratory protection, the full mist and clearance-time rule, cleaning and symptom reporting. Supervisors must hold work for failed extraction or unknown product and arrange competent exposure and health advice. A practical observed spray task, biological-monitoring review and follow-up after a symptom report provide stronger evidence than course attendance.
| Role | Learning and decision | Demonstration and assessor | Record and reassessment trigger |
|---|---|---|---|
| Sprayer | Identify product, set booth, use air-fed RPE and respect clearance time. | Supervisor observes a real setup, spray and stop decision. | Authorisation and equipment checks; refresh after product or booth change. |
| Bystander or cleaner | Recognise mist/clearance zones and report symptoms. | Supervisor tests access and cleaning scenario. | Briefing and route; revisit after task change. |
| Supervisor | Check COSHH, booth/air supply, exclusion, monitoring and symptom response. | Competent manager observes hold and restart decision. | Task check and action record; reassess after failure or case. |
| Occupational health and safety specialists | Interpret surveillance, biological monitoring and control data within competence. | Clinical or technical peer reviews a case and controls. | Confidential health and technical records; review on new evidence. |
How should management check and improve these controls?
HSE’s Plan, Do, Check, Act approach helps an organisation plan controls, put them into use, check performance and correct failures. It is management guidance, not a substitute for the GB or Northern Ireland legal duties that apply to the task.
Link product identity, spray control, booth testing, respiratory protection, biological monitoring and symptoms to corrective action. Stop spray work when control evidence fails. HSE management guidance
What warning signs show isocyanate controls are weak?
Warning signs include symptoms, visor lifting, unknown products, no monitoring and weak booth control.
A spray-booth fault, visor lift, missing clearance-time evidence or work-related wheeze requires the supervisor to stop exposure, protect bystanders and arrange appropriate health advice. Reopen only after the product, booth, air supply and method have been checked.
- Spraying outside booth — High-risk exposure may be uncontrolled. Stop and reassess method.
- Visors lifted in booth/room — Worker may inhale mist. Retrain, improve visibility and supervise.
- No biological monitoring — Control effectiveness may be assumed. Introduce competent monitoring programme.
- Workers report night symptoms — Possible work-related asthma pattern. Remove from exposure and refer to OH/medical route.
- No clearance time displayed — People may enter too early. Measure, display and brief clearance time.
Chemical hazard symbols: what do they mean?

Exploding bomb
Explosive, self-reactive or organic peroxide hazards.

Flame
Flammable, self-heating or pyrophoric substances.

Flame over circle
Oxidising substances that can intensify fire.

Gas cylinder
Gas under pressure.

Corrosion
Skin burns, eye damage or corrosive to metals.

Skull and crossbones
Acute toxicity.

Exclamation mark
Irritation, harmful effects or skin sensitisation; some classifications cover drowsiness, dizziness or ozone-layer hazard. Read the actual hazard statements. Skin sensitisation differs from respiratory sensitisation.

Health hazard
Serious health hazards, including organ damage, aspiration hazard, respiratory sensitisation, cancer and reproductive effects; some can follow a single exposure.

Environment
Hazardous to the aquatic environment.
What do the acronyms and key terms mean?
These terms explain the decisions used in this page.
| Acronym | Meaning | Plain-English use |
|---|---|---|
| COSHH | Control of Substances Hazardous to Health | Regulations and framework for hazardous substance control. |
| RPE | Respiratory Protective Equipment | Equipment that protects against inhaled exposure. |
| BA | Breathing Apparatus | Respiratory protection supplied with breathable air. |
| LEV | Local Exhaust Ventilation | Engineering control to capture airborne contaminants. |
| WEL | Workplace Exposure Limit | In Great Britain, an approved workplace exposure limit is a legally binding airborne exposure limit. A biological monitoring guidance value is a different control-performance guide, not a WEL. Use the separate NI COSHH route for NI work. |
| OH | Occupational health | Work-focused health support and surveillance. |
Unlock another resource
You have used this month’s two free downloads. Publish a post in your own words to unlock one more resource, or choose SHARE Individual for 10 downloads per month.
You decide whether to share. If you do, use the relevant platform disclosure tools and do not make claims you do not genuinely hold.