
SHARE Knowledge Hub
Occupational Asthma
Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure. Flour dust, isocyanate spray mist and other workplace agents can inflame and narrow the airways, with symptoms sometimes appearing after a shift. In Great Britain and Northern Ireland, early recognition and control of exposure matter because continued contact can leave lasting symptoms and may prevent a return to the same work.
Understanding Occupational Asthma
Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure. Flour dust, isocyanate spray mist and other workplace agents can inflame and narrow the airways, with symptoms sometimes appearing after a shift. In Great Britain and Northern Ireland, early recognition and control of exposure matter because continued contact can leave lasting symptoms and may prevent a return to the same work.
Why this matters at work
NI COSHH and HSENI guidance require a health-surveillance decision when the agent can cause disease, early detection and action are possible, and workplace conditions make disease likely. For isocyanate spraying and other credible asthmagen exposure, arrange a competent occupational-health scheme that covers the exposed groups, including cleaners and people outside the normal spray team. A symptom questionnaire or spirometry visit cannot substitute for source control.
The hazard is exposure to a respiratory sensitiser such as isocyanate mist, flour dust, wood dust or an enzyme. Possible harms include sensitisation, recurrent asthma attacks and persistent work disability; existing asthma may also be made worse by work. Barriers include hidden ingredients, changing products, short spray or cleaning peaks, failed extraction, unmeasured booth clearance, poor RPE fit, delayed symptoms and worker concern about reporting.
How organisations manage this in practice
COSHH requires prevention of hazardous exposure where reasonably practicable, or adequate control using good control practice. HSE states that for asthmagens exposure should be reduced as low as reasonably practicable, including where a workplace exposure limit exists. A result below a WEL is not a safe threshold for a sensitised worker, nor proof that all peak tasks and bystanders were protected.
A WEL comparison is one component of control, not proof that sensitisation risk has vanished. Identify the asthmagen, physical form, task and release routes and check normal work, peaks, maintenance and nearby workers. HSE guidance requires exposure to respiratory sensitisers to be reduced as low as reasonably practicable as well as meeting applicable limits.
Tell workers why surveillance is offered, how confidentiality works and how to report symptoms between scheduled checks. Define who tells the employer when controls require review and who contacts a worker needing clinical assessment. Reconsider coverage after new products, a process change, a positive exposure result or a case, not merely on contract renewal.
How can I practise this topic in 3D?


Booth 1: isocyanate spray mist
All related inspection points 2 across 1 location
Garage workshop 2 inspection points
Practice in the SHAREhub environment. Browser practice is separate from workplace competence and formal learning records.
What is occupational asthma and how does harm develop?
Occupational asthma is new asthma caused by workplace exposure. Most cases involve sensitisation to a respiratory sensitiser, or asthmagen; a substantial irritant exposure can cause a different work-related asthma pattern. Work-aggravated asthma means existing asthma is made worse by work and also needs a control response. HSE asthmagen guidance
Best-practice guide: Occupational Asthma

What is occupational asthma and how does harm develop?
Occupational asthma is new asthma caused by workplace exposure. Most cases involve sensitisation to a respiratory sensitiser, or asthmagen; a substantial irritant exposure can cause a different work-related asthma pattern. Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure.
Turn occupational asthma knowledge into a decision
Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure. Flour dust, isocyanate spray mist and other workplace agents can inflame and narrow the airways, with symptoms sometimes appearing after a shift. Treat as possible work-related pattern and refer.
Bakery occupational asthma scenario
Symptoms improve away from work: Treat as possible work-related pattern and refer. HSE FLOUR Open flour tipping: Review enclosed or low-dust transfer. HSE FLOUR
Work exposure and asthma harm mechanisms
Exposure route 1: Flour or enzyme dust during tipping, mixing or dry cleaning Airborne particles enter the breathing zone; in susceptible people the airways may become sensitised and inflamed. Exposure route 2: Isocyanate-containing spray mist during coating or booth entry Fine mist reaches workers inside or outside a poorly controlled spray room; sensitisation can make later low exposures trigger asthma. High-level irritant gas, vapour or fume release: A substantial acute inhalation can inflame airways without the usual sensitisation delay; clinical assessment determines the disease pattern.
Choose controls for occupational asthma
Elimination: Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible. Substitution: Validate a suitable low-dust flour or improver form while checking allergenic, skin, quality and process hazards. Engineering controls: Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work. Engineering controls: Provide effective capture and suitable mixer covers or contained charging; use dust-controlled cleaning instead of dry sweeping. Administrative controls: Use a low-release charging method and realistic quantities; include maintenance, exposure review and required health surveillance in the plan. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Use the full occupational asthma lesson
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.

Read all six steps as text
1. What is occupational asthma and how does harm develop?
Occupational asthma is new asthma caused by workplace exposure.
- Avoid / redesign: Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible.
- Control the task: Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work.
- Verify before release: If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls.
Occupational asthma is new asthma caused by workplace exposure. Most cases involve sensitisation to a respiratory sensitiser, or asthmagen; a substantial irritant exposure can cause a different work-related asthma pattern. Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure.
Apply it: Which part of this plan would you check at the workface before authorising the task?
2. Turn occupational asthma knowledge into a decision
Use the evidence to improve the actual work arrangement.
- Change at source: Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible.
- Make it observable: If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls.
- Keep useful evidence: Treat as possible work-related pattern and refer.
Occupational asthma is new asthma caused by inhaling a respiratory sensitiser at work or, in some cases, by a high-level irritant exposure. Flour dust, isocyanate spray mist and other workplace agents can inflame and narrow the airways, with symptoms sometimes appearing after a shift. Treat as possible work-related pattern and refer.
Apply it: What evidence would show that the change improves this task, rather than only completing a record?
3. Bakery occupational asthma scenario
Example: a practical application of the existing topic lesson.
- Symptoms improve away from work: Treat as possible work-related pattern and refer.
- Open flour tipping: Review enclosed or low-dust transfer.
- Dry sweeping: Use suitable vacuum and wet/controlled cleaning.
Symptoms improve away from work: Treat as possible work-related pattern and refer. HSE FLOUR Open flour tipping: Review enclosed or low-dust transfer. HSE FLOUR
Apply it: At which point would you hold this example, and what evidence would allow it to proceed?
4. Work exposure and asthma harm mechanisms
Connect the task, the route to the person and the control that can fail.
- Exposure route 1: Flour or enzyme dust during tipping, mixing or dry cleaning Airborne particles enter the breathing zone; in susceptible people the airways may become sensitised and inflamed.
- Exposure route 2: Isocyanate-containing spray mist during coating or booth entry Fine mist reaches workers inside or outside a poorly controlled spray room; sensitisation can make later low exposures trigger asthma.
- High-level irritant gas, vapour or fume release: A substantial acute inhalation can inflame airways without the usual sensitisation delay; clinical assessment determines the disease pattern.
Exposure route 1: Flour or enzyme dust during tipping, mixing or dry cleaning Airborne particles enter the breathing zone; in susceptible people the airways may become sensitised and inflamed. Exposure route 2: Isocyanate-containing spray mist during coating or booth entry Fine mist reaches workers inside or outside a poorly controlled spray room; sensitisation can make later low exposures trigger asthma. High-level irritant gas, vapour or fume release: A substantial acute inhalation can inflame airways without the usual sensitisation delay; clinical assessment determines the disease pattern.
Apply it: Who could be exposed, including other trades, cleaners, maintainers and people nearby?
5. Choose controls for occupational asthma
Start with the stronger practicable options and verify their effect.
- Elimination: Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible.
- Substitution: Validate a suitable low-dust flour or improver form while checking allergenic, skin, quality and process hazards.
- Engineering controls: Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work.
- Engineering controls: Provide effective capture and suitable mixer covers or contained charging; use dust-controlled cleaning instead of dry sweeping.
- Administrative controls: Use a low-release charging method and realistic quantities; include maintenance, exposure review and required health surveillance in the plan.
Elimination: Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible. Substitution: Validate a suitable low-dust flour or improver form while checking allergenic, skin, quality and process hazards. Engineering controls: Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work. Engineering controls: Provide effective capture and suitable mixer covers or contained charging; use dust-controlled cleaning instead of dry sweeping. Administrative controls: Use a low-release charging method and realistic quantities; include maintenance, exposure review and required health surveillance in the plan. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Apply it: Which stronger option can be used here, and who will verify it before accepting the remaining risk?
6. Use the full occupational asthma lesson
Follow the official sources below and retain the task-specific evidence.
- Official guidance: HSE: Asthma: an overview
- Official guidance: HSE substances that can cause occupational asthma
- Task decision: Treat as possible work-related pattern and refer.
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.
Apply it: Which official source and full-topic section will you use to resolve the next decision?
Flour dust, isocyanates, some wood dusts, solder flux fume, enzymes and animal allergens are examples of agents that need task-specific assessment. Inhaled material can inflame and narrow the bronchial airways. After sensitisation, a small later exposure may trigger cough, wheeze, chest tightness or breathlessness; symptoms can appear during a shift or hours later at night.
A pattern that eases during weekends or holidays is a useful clue, but it is not a diagnosis and absence of that pattern does not rule work out. Nasal or eye irritation may appear early. Continued exposure after symptoms start can reduce the chance of recovery, so report the task and timing promptly, control exposure and seek clinical assessment. Severe breathing difficulty needs urgent help.
| Source and task | Route and body effect | Outcome and early warning | Stop or escalate when |
|---|---|---|---|
| Flour or enzyme dust during tipping, mixing or dry cleaning | Airborne particles enter the breathing zone; in susceptible people the airways may become sensitised and inflamed. | Rhinitis, cough, wheeze or chest tightness may precede persistent asthma; symptoms can appear after work. | Visible dust, work-linked symptoms or failed extraction: stop dusty handling, control the release and arrange prompt clinical/OH advice. |
| Isocyanate-containing spray mist during coating or booth entry | Fine mist reaches workers inside or outside a poorly controlled spray room; sensitisation can make later low exposures trigger asthma. | Evening or night symptoms, worsening reliever use or surveillance changes may signal disease; ongoing exposure can leave lasting impairment. | Spray outside the assessed booth, ineffective extraction, premature entry or symptoms: stop exposure and get competent booth and health review. |
| High-level irritant gas, vapour or fume release | A substantial acute inhalation can inflame airways without the usual sensitisation delay; clinical assessment determines the disease pattern. | Immediate breathing symptoms may be serious; later persistent asthma is possible after a major exposure. | Evacuate or isolate by the emergency plan, obtain urgent medical help for severe breathing difficulty and do not restart before investigation. |
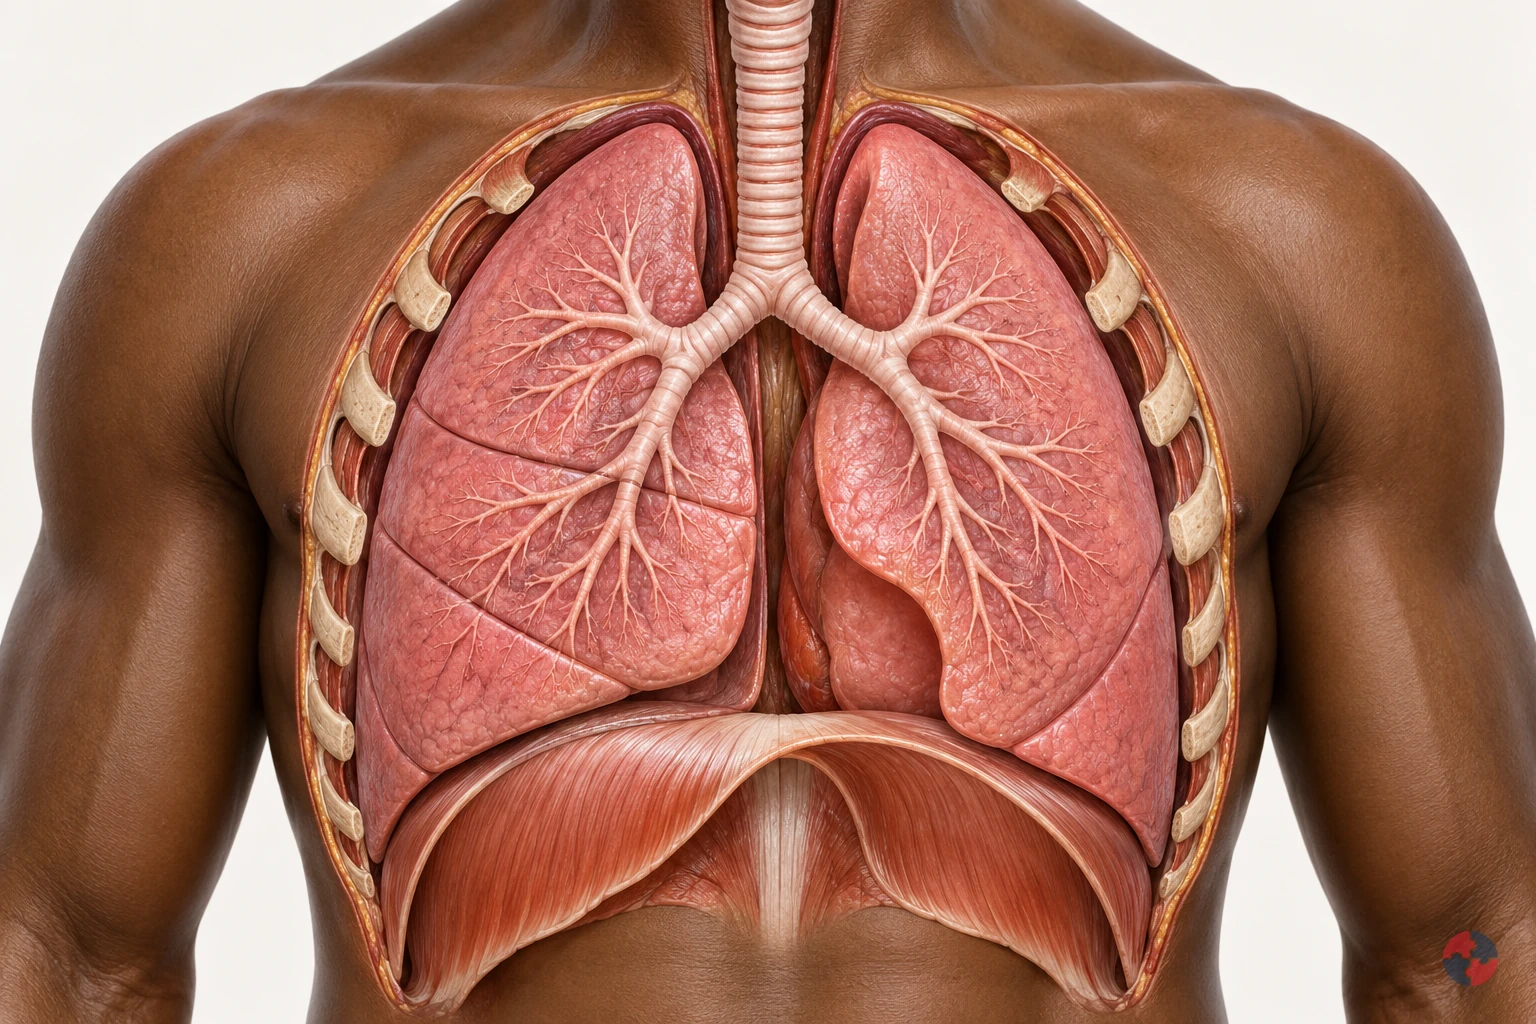
How do the lungs work, and how can workplace exposures affect breathing?
Interactive anatomy · Respiratory tract and lungs · Updated 2026-10-23
Read all anatomy and process explanations without the viewer
Simplified education, not diagnosis, a lung-function or oxygen-saturation test, an exposure calculator or a fitness-to-work assessment. No breath-holding challenge, breathing-rate score or personal health-data collection. Ordinary particle filters do not protect against every gas or oxygen deficiency. COPD and coal-dust topics may reuse normal anatomy only until separate mechanisms are reviewed.
Nose and mouth
Air enters and leaves here. The nose and mouth connect the outside air with the respiratory passages. Air moves through these openings on both the inward and outward breath. Follow the route towards the windpipe before looking at the smaller branches. The illustrated flow is air, a mixture of gases, rather than pure oxygen passing directly into blood. Frimley Health NHS Foundation Trust: How your lungs work · Central and North West London NHS Foundation Trust: How do we breathe?
Trachea
The windpipe carries air into the chest. The trachea, commonly called the windpipe, carries air down towards the chest. It divides into the two main bronchi that supply the lungs. Locate this shared passage before following either branch. Its role is to conduct air towards the gas-exchange regions and provide an outward route for the next exhalation. Frimley Health NHS Foundation Trust: How your lungs work
Bronchi
A main branch carries air into each lung. The two main bronchi take air from the windpipe into the right and left lungs. They divide into progressively smaller branches, distributing the breath through the lungs. Use the split as a landmark before following one highlighted route. These are air passages, distinct from the blood vessels that run through the same organs. Frimley Health NHS Foundation Trust: How your lungs work · University Hospitals of North Midlands NHS Trust: My lung surgery: about your lungs
Bronchioles
Smaller branches distribute air. Bronchioles are smaller branches of the airway system inside the lungs. Their branching routes lead towards clusters of alveoli, where the breath reaches the gas-exchange surface. Follow one branch to its end, using the others as context. This simplified route represents part of a much larger network supplying the lungs together. Frimley Health NHS Foundation Trust: How your lungs work
Alveoli
Tiny air sacs provide a gas-exchange surface. Alveoli are tiny air sacs at the ends of the small airway routes. Their close relationship with surrounding capillaries allows oxygen to pass towards blood and carbon dioxide towards alveolar air. Connect the highlighted cluster with the enlarged gas-exchange view. The enlargement changes the scale so the air space and neighbouring blood vessel can be distinguished. Frimley Health NHS Foundation Trust: How your lungs work · Central and North West London NHS Foundation Trust: How do we breathe?
Air–blood barrier
A thin boundary separates air from blood. The thin alveolar and capillary walls separate air in the sac from blood in its neighbouring vessel. Oxygen and carbon dioxide cross this boundary in opposite directions. Locate the tissue between the two spaces in the enlarged view. Blood cells remain in the vessel; the model does not represent an open connection through which air and blood mix. Central and North West London NHS Foundation Trust: How do we breathe?
Pulmonary capillaries
Small blood vessels pass beside the air sacs. Pulmonary capillaries are small blood vessels beside the alveoli. Blood moving through them receives oxygen and releases carbon dioxide across the thin exchange boundary, then continues through the circulation. Follow the labelled gas routes separately from the blood cells. These cells stay inside the capillary rather than moving into the air sac. Central and North West London NHS Foundation Trust: How do we breathe?
Diaphragm
This muscle helps make room for a breath. The diaphragm is a broad, dome-shaped breathing muscle beneath the lungs. It contracts and flattens downwards during inhalation, helping increase the space in the chest. During a quiet exhalation it relaxes towards its dome shape. Compare it with the rib cage: their changing positions help move air without the lung tissue acting as a contracting muscle. Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
Rib cage and breathing muscles
Chest movement changes the space around the lungs. The rib cage protects the chest organs and moves with the breathing muscles. Expansion upwards and outwards helps increase chest space during inhalation; relaxation reduces that space during a quiet exhalation. Compare this movement with the diaphragm below the lungs. Together these structures provide the mechanics that allow air to move through the airways. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
Pleura
Two thin layers surround the lungs and line the chest. The pleura has two thin layers around the lungs and inside the chest wall. A small amount of fluid between them allows the surfaces to slide with less friction as breathing changes the chest space. Locate this outer covering separately from the internal air sacs; it is not the thin air–blood exchange boundary. Blackpool Teaching Hospitals NHS Foundation Trust: Pleural clinic
Open the complete process transcript
The process, step by step
1 · Make space
Breathing in begins with a change in the space inside the chest. The diaphragm, a dome-shaped muscle beneath the lungs, contracts and moves downwards. Muscles around the ribs help lift the chest upwards and outwards. As the lungs expand with this changing space, air can enter through the airways. Locate the diaphragm and rib cage together rather than treating the lungs as muscles that pull themselves open. The model separates the movement into a teaching step so you can follow its purpose. In the body, chest movement, airflow and blood circulation are connected parts of a continuing process. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
What to watch: Locate the diaphragm beneath the lungs and the rib cage around them; compare their positions with the space occupied by the lungs.
Why it matters: Changing the chest space draws air into the lung passages. The breathing muscles supply the movement, while the lungs expand with the chest to receive the next breath.
Explore this step: Select the diaphragm and rib cage in turn, then explain how their movement helps air enter without the lungs contracting like muscles.
2 · Move air
Air entering through the nose or mouth travels down the trachea, or windpipe, towards the chest. The trachea divides into the two main bronchi, with one route supplying each lung. Follow this continuous passage in the whole-chest view before moving into the smaller branches. The moving air is a mixture of gases, including oxygen; it is not a stream of pure oxygen travelling straight into the blood. These larger airways carry the breath towards the places where gas exchange happens. The same connected passages also provide the outward route when air is breathed out. Frimley Health NHS Foundation Trust: How your lungs work
What to watch: Start at the nose and mouth, follow the trachea downwards and find the split into the right and left main bronchi.
Why it matters: The larger passages distribute air to both lungs and connect the outside air with the smaller branches inside. Gas exchange takes place further along the route, rather than within the windpipe.
Explore this step: Trace the route to each lung and distinguish the tubes carrying air from the separate vessels carrying blood.
3 · Reach the air sacs
Inside each lung, the bronchi divide into smaller branches called bronchioles. These passages distribute air towards clusters of tiny air sacs, the alveoli. Follow one branch in the close-up and connect its end with an air-sac cluster, using the other branches as surrounding context. These routes distribute the breath throughout the lungs rather than supplying only one working air sac. A real lung contains many branching routes and air sacs operating together. This distribution brings air close to a large network of small blood vessels, preparing for the exchange shown in the next view. Frimley Health NHS Foundation Trust: How your lungs work
What to watch: Follow one smaller airway to the cluster of air sacs at its end, keeping the other branches as surrounding context.
Why it matters: Branching delivers air throughout the lungs instead of to one large chamber. The many air sacs bring the inhaled gases close to blood vessels where oxygen and carbon dioxide can cross.
Explore this step: Trace one complete branch to its air sacs, then explain how the many branches distribute air throughout the lungs.
4 · Change scale
The lesson now changes from a branching airway to an enlarged air–blood interface. An alveolus contains air; beside it runs a capillary containing blood. Their very thin walls form the boundary across which gases can move. Locate the air space, the separating tissue and the inside of the vessel before following any gas symbols. The magnified view represents a tiny part of the same lung, not a separate organ or a hole that joins air and blood into one space. The enlargement helps explain how the two systems can exchange gases while keeping their contents separate. Central and North West London NHS Foundation Trust: How do we breathe?
What to watch: Find the air inside the enlarged alveolus, the thin separating boundary and the neighbouring capillary with blood cells inside it.
Why it matters: A close boundary allows gases to cross between alveolar air and capillary blood. Keeping the two spaces separate lets ventilation and circulation cooperate without blood cells entering the air sac.
Explore this step: Identify the air space and blood-vessel space, then point to the boundary each gas must cross between them.
5 · Exchange gases
At the air–blood boundary, oxygen moves from the alveolar air into the capillary blood. At the same time, carbon dioxide carried back from the body moves from the blood into the air sac. The two gases cross in opposite directions; blood cells stay within the vessel. Follow each labelled symbol separately so that exchanging gases is not confused with mixing the air and blood together. Blood then carries oxygen onwards towards the heart and the body’s tissues. The teaching symbols simplify continuous gas movement, and their size, colour and speed do not represent a measurement. Central and North West London NHS Foundation Trust: How do we breathe?
What to watch: Follow the O₂ symbol towards the capillary and the CO₂ symbol towards the air sac, while locating the blood cells within the vessel.
Why it matters: Oxygen can be carried onwards for use by the body, while carbon dioxide returns to the airways for removal. Both transfers connect the breath with the continuing circulation of blood.
Explore this step: Trace the two gas routes in opposite directions and explain why a blood cell should remain inside the capillary.
6 · Breathe out
During a quiet breath out, the diaphragm and other breathing muscles relax. The diaphragm returns towards its dome shape, chest space decreases and air moves back along the airways to the nose or mouth. This outgoing air carries carbon dioxide that crossed from the blood into the alveoli. Trace the route in reverse without reversing the direction of blood circulation: oxygen-carrying blood continues towards the heart while another breath prepares to enter. The model presents a single cycle to explain the relationship. It does not show breathing as a series of separate events in which circulation stops between steps. Central and North West London NHS Foundation Trust: How do we breathe? · Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved
What to watch: Compare the diaphragm and chest with the inhalation step, then follow the outward airway route from the lungs to the nose or mouth.
Why it matters: Exhalation removes air containing carbon dioxide from gas exchange. Meanwhile, blood circulation continues carrying oxygen onwards, linking this breathing cycle with the needs of the rest of the body.
Explore this step: Trace the outward air route and the onward blood route separately, then describe why they are connected processes with different pathways.
Mechanisms and their limits
Sensitiser-related asthma Some people become sensitised to workplace substances such as flour or wood dust. Later exposure may trigger inflamed, narrowed airways, sometimes at low levels. Compare the airway opening, not the size of the whole lung. Sensitisation and later triggering are different phases, shown without a fixed clock. Work can also worsen existing asthma. Not all work-related asthma is an allergic reaction. A symptom pattern can prompt investigation but cannot establish a diagnosis from this model. HSE: Asthma: an overview · NHS: Asthma · HSE: Flour dust and risks to bakers
Assess sensitisers and maintain exposure controls
Get clinical advice about asthma symptoms
Sensitiser-related asthma — follow the anatomy
Look at: The airway opening, its muscle and swollen lining.
What changes: In asthma, narrowing, swelling and mucus can restrict the route for air.
Why it matters: Breathing may become difficult, with wheeze, cough or chest tightness.
What to do: Prevent exposure to the cause and report breathing symptoms for medical assessment.
Flour handling and later occupational asthma
Bakery: flour is tipped and benches are dusted repeatedly during production. Time jump: sensitisation may develop over a variable period; a later exposure may trigger symptoms. This is not asthma developing in 32 seconds. Not every exposed or sensitised person develops asthma. Wheeze or timing alone does not establish the cause or diagnosis.
A dusty bakery task Flour is tipped into a mixer and used to dust the bench. Review low-dust ingredients and careful handling before relying on the worker to avoid a visible cloud. HSE: Flour dust and risks to bakers
Repeated exposure, then a time jump Breathing flour dust can lead to sensitisation in some people over time. The timeline now jumps to a later contact after a hypersensitive state has developed in this chosen example. HSE: Asthma: an overview · HSE: Flour dust and risks to bakers
A later contact can narrow airways The airway wall becomes inflamed and the breathing passage narrows in the illustrative asthma episode. Symptoms may occur during the task or later; this is not the same as identifying asthma by a short animation. HSE: Asthma: an overview · NHS: Asthma
Report patterns and reduce exposure Report work-related breathing problems promptly and obtain clinical advice. Review low-dust flour, transfer/handling and the full control assessment; use the emergency panel immediately for severe breathing difficulty. HSE: Advice for employers: occupational asthma · HSE: Flour dust and risks to bakers · NHS: Shortness of breath
Read the practice situations and all answer explanations
LU-Q1: Which plan best addresses the hazard?
A team plans repeated concrete cuts with a handheld cut-off saw. Dust can enter the operator’s and nearby workers’ breathing zones.
Open a window and use the same dry-cutting method. — A window alone does not control dust generated beside the face. Choose task controls that prevent or capture it at source.
First reduce the need to cut, then assess source suppression or extraction and any required suitable RPE. — This addresses the task before exposure occurs. Check that suppression or extraction works and that required RPE is suitable, fitted and used.
Continue while nobody is coughing. — Symptoms are not an exposure monitor. Harmful respirable dust may be invisible, and a worker can feel well during exposure.
HSE: Construction dust: cutting paving blocks, kerbs and flagsLU-Q2: What is the most useful next action?
A bakery worker notices repeated wheeze after dusty flour tasks, including some symptoms later in the evening.
Report the pattern and seek medical and workplace assessment. — Reporting the pattern allows exposure controls and clinical assessment to be reviewed. Symptoms can be delayed; a clinician may need further investigation.
Use this model to diagnose occupational asthma. — The model explains a mechanism. It cannot diagnose asthma or establish that work caused it.
Assume the task is safe if breathing improves away from work. — Improvement away from work may be useful information for investigation, but it does not show that returning to the same exposure is safe.
HSE: Asthma: an overview · HSE: Advice for employers: occupational asthma · NHS: Asthma · HSE: Flour dust and risks to bakersLU-Q3: What is the important distinction?
One diagram shows a narrowed airway at LUN03–04. A second shows scarred gas-exchange tissue around LUN05–07.
They show the same disease at successive stages. — Narrowed airways and scarred lung tissue are different changes. One is not automatically the next stage of the other.
Both effects disappear when airborne dust settles. — Removing airborne dust does not reverse established fibrosis. Controlling further exposure remains important.
Airway narrowing and tissue fibrosis are different mechanisms. — Correct. Airway narrowing affects the passage for air; fibrosis affects lung tissue and its function. Neither picture supplies an individual diagnosis.
NHS: Silicosis · NHS: AsthmaSources and how the model is made
The opening images are AI-generated anatomical illustrations. The interactive 3D models and labelled SVG diagrams use original procedural artwork. These teaching images are not medical scans or diagnostic tools. Source references support the learner explanations and do not grant artwork rights.
- Frimley Health NHS Foundation Trust: How your lungs work — Normal airway branching, air sacs and capillary gas exchange; factual text only.
- Central and North West London NHS Foundation Trust: How do we breathe? — Thin alveolar/capillary walls, opposing gas transfer, circulation and chest mechanics. No illustrations or exercises copied.
- Cambridge University Hospitals NHS Foundation Trust: Breathing techniques to ease breathlessness: muscles involved — Diaphragm movement and breathing-muscle context only; this module does not prescribe breathing exercises.
- HSE: Health risks from welding — Welding-related airway irritation, possible deeper injury and irritant asthma; not a universal pattern for every gas.
- HSE: Asthma: an overview — Sensitisation, later triggering and work aggravation. Legacy labelling language and statistics are not reused.
- HSE: Advice for employers: occupational asthma — Exposure prevention, controls and health surveillance only; legacy legislation wording is not reused.
- NHS: Silicosis — Silica-associated inflammation/fibrosis, varying latency, irreversible damage and possible progression after exposure stops.
- HSE: Why is asbestos dangerous? — Asbestosis, mesothelioma and pleural disease are distinct; long disease latency.
- HSE: Construction dust: cutting paving blocks, kerbs and flags — Task design, source suppression/extraction, suitable RPE and checking controls; not a generic dust safe-dose rule.
- NHS: Shortness of breath — Emergency recognition of severe breathing difficulty and 999; emergency advice is outside the activity.
- NHS: Asthma — Narrowed/swollen airways, symptoms and clinical diagnosis; no medication doses or treatment plan reproduced.
- University Hospitals of North Midlands NHS Trust: My lung surgery: about your lungs — Right/left lung lobe counts and airway anatomy; no source image copied.
- Blackpool Teaching Hospitals NHS Foundation Trust: Pleural clinic — Pleural layers and the small lubricating fluid layer outside lung tissue; no procedural teaching included.
- HSE: Asphyxiation hazards in welding and allied processes — Oxygen-deficient spaces and need for independent air supply; no unprotected entry or rescue.
- HSE: Respiratory protective equipment at work — RPE selection must match the contaminant and conditions; filtering protection is not a supply of oxygen.
- HSE: Flour dust and risks to bakers — Flour sensitisation and practical reduction of dusty handling; exposure-limit numbers are not reused.
- Health and Safety Executive: Asbestos essentials — Task planning, training and competent asbestos work arrangements for the maintenance exposure example; not permission to disturb unknown material or a licence/classification decision.
- Health and Safety Executive: Welding fume: protect your workers — Alternative joining, fume reduction, LEV, suitable RPE and maintained controls for the welding-fume example. No unprotected exposure or rescue procedure.
How should COSHH control occupational asthma risk?
Name the actual respiratory sensitiser and every task that releases it. A COSHH assessment that says only “dust” or “chemical” cannot distinguish flour, wood dust, isocyanate mist or an enzyme. Identify workers and others nearby, routine and maintenance work, skin and inhalation routes, control failures, symptoms and the product information needed to choose a safer method.
Use control hierarchy as a planning sequence, not a statute: eliminate the harmful step where feasible, reduce or substitute it, isolate it, then use engineering controls before administrative rules and RPE. For a bakery, lower-dust flour and enclosed transfer can prevent a cloud at source; a disposable mask alone does not correct open tipping or dry sweeping. For isocyanate spraying, a properly designed booth, clearance control and air-fed protection are task-specific requirements that need competent verification.
Health surveillance can detect early signs when workers remain exposed or likely to be exposed to asthmagens, but it does not capture airborne material. Work-linked symptoms, an abnormal surveillance finding or a control defect require an exposure and clinical response together. A competent occupational hygienist should decide whether sampling is needed and how results affect the control plan.
| Asthmagen or sector | Typical exposure | Control focus |
|---|---|---|
| Flour dust | Mixing, tipping, sieving, dusting and cleaning in bakeries. | Low-dust methods, enclosed transfer, LEV and no dry sweeping. HSE FLOUR |
| Isocyanates | Spray painting, 2K products, foam and coating work. | Substitution, spray booth, air-fed RPE, clearance time and surveillance. HSE MVR |
| Wood dust | Cutting, sanding, machining and cleaning. | LEV, on-tool extraction, housekeeping and surveillance. HSE ASTHMAGENS |
| Solder flux or rosin fume | Soldering and electronics work. | Tip extraction, LEV and process control. HSE ASTHMAGENS |
| Laboratory animal allergens | Animal handling, cage cleaning, bedding and laundry. | Containment, ventilation, work method and surveillance. HSE ASTHMAGENS |
| Enzymes and cleaning agents | Detergent, food, healthcare and cleaning work. | Substitution, dilution, closed systems and spray control. HSE ASTHMAGENS |
For the actual task hazard, HSE places elimination first, then substitution, engineering controls, administrative controls and suitable PPE for residual risk. Record why a higher control is not practicable and how the chosen measure is checked in use. HSE hierarchy of controls
Use the HSE hierarchy for this task: eliminate the hazard where possible, substitute, use engineering controls, organise the work and use suitable PPE for residual risk. The exact choices require a task-specific assessment and competent verification. HSE hierarchy of controls
| Sector, task and people | Exposure route and harm | Strongest feasible controls | Residual safeguard and stop check |
|---|---|---|---|
| Manufacturing: vehicle-paint sprayers and nearby staff | Isocyanate mist can escape spraying and cause sensitisation or worsen existing asthma. | Avoid isocyanate use where feasible; use a designed booth, verified clearance and competent air-fed RPE. | Check booth integrity, clearance and biological/health monitoring where indicated; stop for leakage or symptoms. HSE MVR |
| Construction: joiners, cleaners and others near timber cutting | Some wood dust can reach airways and cause asthma; sweeping may re-suspend dust. | Use less dusty methods, on-tool extraction and segregation; avoid dry sweeping. | Inspect extraction and housekeeping; stop dusty cutting when controls fail. HSE ASTHMAGENS |
| Hospitality and food production: bakers and cleaners | Flour and enzyme dust from tipping, dusting and clean-up can sensitise workers. | Use low-dust materials, closed or low-drop handling and effective extraction. | Observe flour clouds and work-linked symptoms; stop the dusty step and review surveillance. HSE FLOUR |
| Laboratories and animal facilities: handlers and laundry staff | Animal proteins in aerosols or contaminated bedding can sensitise airways. | Use enclosure, ventilated handling and controlled bedding/laundry transfer. | Check access, ventilation and symptoms; hold work for containment failure. HSE ASTHMAGENS |
How do the same controls apply to other material hazards?
Each row applies elimination, substitution, engineering, administrative checks and residual personal protection to the work hazard. The five HSE levels are elimination, substitution, engineering controls, administrative controls and PPE; supervision and inspection support the administrative arrangements. A higher control may be infeasible only after the specific task and alternative have been assessed.
| Hazard | Eliminate, substitute, engineer | Admin, PPE, owner and check | Failure, stop and direct sources |
|---|---|---|---|
| Acute irritant gas or vapour release | Eliminate the mixing or transfer that produces the release if the process can change; otherwise test a lower-hazard product and verify it does not create another reaction. Enclose transfer, segregate the release area and provide designed capture or emergency ventilation. | COSHH owner checks product information, containment, extraction and detector/air results before start and after change; train for foreseeable release. Emergency RPE is only for a trained, authorised response, not routine entry. administrative supervision and checking sustain engineering and drills. | Stop mixing, withdraw and prevent entry for a leak, failed ventilation, alarm or symptoms; use the site emergency plan and competent responders, never an unplanned rescue.HSE ASTHMAGENS HSE PPE HIERARCHY HSENI COSHH |
How can bakery flour dust cause occupational asthma?
A bakery scenario shows why visible flour dust, cleaning methods and symptom patterns must be treated as control evidence. HSE FLOUR
A bakery uses open flour tipping, hand dusting and dry sweeping at the end of the shift. A worker reports coughing and chest tightness on workdays, with improvement during a week away. The supervisor says everyone coughs a bit around flour and issues a disposable mask.
A competent response treats flour dust as an asthmagen. It reviews low-dust flour handling, enclosed tipping, dusting technique, LEV, cleaning with suitable vacuum rather than dry sweeping, RPE suitability, worker training, health surveillance and whether other workers have symptoms. The worker is signposted to OH or medical advice and unnecessary health details are kept out of ordinary manager records.
The supervisor holds the dusty tipping and sweeping steps, checks the product and safety data, speaks privately with the affected worker and arranges prompt medical or occupational-health advice. The bakery then trials low-dust flour, enclosed or low-drop transfer and suitable extraction, replaces dry sweeping with controlled cleaning, checks neighbouring workers and records who may restart each task. The flour workplace exposure limit in Great Britain is 10 mg/m³ over 8 hours and 30 mg/m³ over 15 minutes, but HSE says exposure to this asthmagen should be reduced as far below those limits as reasonably practicable; a number is not a safe target. Confirm the current limit and NI application before using it in a formal assessment.
Before restart, a competent person confirms the controls work during real mixing and cleaning, the worker has a clear symptom-reporting route and the surveillance plan is appropriate. A changed flour, enzyme additive, production rate or cleaning contractor triggers a fresh assessment and hand-back.
| Finding | Weak response | Stronger response |
|---|---|---|
| Symptoms improve away from work | Dismissed as seasonal cough. | Treat as possible work-related pattern and refer. HSE FLOUR |
| Open flour tipping | Accepted as traditional practice. | Review enclosed or low-dust transfer. HSE FLOUR |
| Dry sweeping | Creates airborne flour dust. | Use suitable vacuum and wet/controlled cleaning. HSE FLOUR |
| Disposable mask issued | PPE-only control. | Apply hierarchy and select suitable RPE if needed. HSE FLOUR |
| Others may be exposed | Only one worker considered. | Check exposure group and surveillance results. HSE FLOUR |
| No evidence trail | No control review recorded. | Record COSHH review, actions and OH advice summary. HSE FLOUR |
How do occupational asthma, work-aggravated asthma and irritant-induced asthma differ?
The labels matter for clinical assessment, but managers should focus first on exposure control, work impact and early escalation.
Occupational asthma may follow sensitisation to a workplace substance. After sensitisation, very low levels can trigger symptoms, so early reporting and exposure prevention matter. Work-aggravated asthma means existing asthma is worsened by work conditions. Irritant-induced asthma can follow a significant irritant exposure.
A supervisor does not need to decide which label is correct before acting. If symptoms are linked to work, controls and health advice should be reviewed promptly. Common high-risk examples include flour dust, isocyanates, wood dust, solder or rosin fume, cleaning chemicals and laboratory animal allergens.
The distinction is clinically important because sensitiser-induced disease may follow a latency period, while irritant-induced disease can follow a substantial single event. The manager’s immediate decision is the same: prevent further uncontrolled exposure, record the actual task and agent, and refer for competent health assessment rather than assigning a label from one symptom pattern. Cough or irritation alone may not be asthma, but it is still a signal to examine a dusty or fume-producing task. A chlorine or ammonia release, for example, needs an incident response even when no sensitiser has been identified.
How do spirometry and serial peak-flow fit into the pathway?
Respiratory tests can support occupational-health assessment, but managers should not interpret them or delay exposure control while waiting for diagnosis.
Spirometry can help assess lung function, and serial peak-flow records across work periods and rest days can help competent health professionals investigate whether symptoms follow a work-related pattern. These tools need proper instruction, interpretation and confidentiality.
Early reporting matters because continued exposure after sensitisation can make asthma more severe, persistent or disabling. A worker with cough, wheeze, chest tightness or breathlessness linked to work should be removed from uncontrolled exposure and referred through the agreed OH or medical route while the COSHH controls are reviewed.
Serial peak-flow measurements need a suitable work-and-rest pattern and interpretation by a clinician with occupational asthma expertise. A normal single spirometry result or a worker feeling better on holiday does not prove the workplace safe. The employer remains responsible for making, maintaining and retaining the statutory health-surveillance record and permitted fitness outcomes. Confidential clinical notes and detailed tests stay with the OH professional; managers receive only necessary functional and control advice. Secure contracted storage can be used without transferring the employer’s responsibility. If temporary exposure restriction is advised, agree safe alternative work and a fair review route rather than asking the worker to prove a diagnosis first.
For GB COSHH surveillance, keep the health record or a copy available for at least 40 years from its last entry. Define authorised access, worker access and provider-change transfer in the contract. Clinical files transfer securely between OH providers, retaining medical confidence. HSE health-surveillance record keeping; COSHH regulation 11. Keep the separately cited NI statutory route and confirm its applicable record requirements.
What does occupational asthma control look like in spray painting?
Spray-painting controls need process containment, air-fed protection, clearance times, biological monitoring where relevant and health surveillance.
In accident repair or coating work, isocyanate exposure can occur during mixing, spraying, curing, gun cleaning, booth entry and maintenance. Workers outside the booth can also be affected if clearance time or access control is weak.
A good control standard covers product selection, booth airflow, LEV checks, air-fed RPE, face and air-supply checks, clearance time, cleaning method, health surveillance, biological monitoring timing where used and strict defect response.
A spray booth has to be used for its assessed process, with a measured clearance time and controlled entry after spraying. A visor lifted before mist has cleared, a leaking booth or an unprotected cleaner can defeat the system. HSE recommends biological monitoring for vehicle spray painters to check exposure control; the sampling method and timing need specialist advice and do not replace booth or health checks.
| Task stage | Exposure concern | Control standard |
|---|---|---|
| Mixing | Vapour and skin contact during product preparation. | Ventilated mixing area, gloves, eye protection and training. HSE MVR |
| Spraying | Aerosol inhalation and overspray. | Spray booth, air-fed RPE and trained sprayer. HSE MVR |
| Curing and clearance | Residual aerosol or vapour remains in booth. | Observe booth clearance time before entry. HSE MVR |
| Cleaning | Solvent and isocyanate residue exposure. | Controlled cleaning method and RPE/PPE review. HSE MVR |
| Health surveillance | Early symptoms may indicate sensitisation. | OH programme and prompt symptom escalation. HSE MVR |
When should occupational asthma concerns be escalated?
Escalation is needed when symptoms are linked to work, an asthmagen is uncontrolled, health surveillance raises concern, LEV or RPE fails, or a high-level irritant exposure occurs. HSE EMPLOYERS
Workers should be encouraged to report early symptoms without fear of blame or job loss. Early removal from exposure or control improvement can make a major difference.
Managers should use occupational health, occupational hygiene and competent COSHH advice rather than attempting to diagnose or handle respiratory disease informally.
For a severe asthma attack or rapidly worsening breathing, use the emergency plan and urgent medical help. For new work-linked symptoms, stop uncontrolled exposure, seek prompt medical/OH assessment and investigate the task and other exposed workers. Do not wait for a confirmed diagnosis before correcting a defective booth, extractor or cleaning method; do not let a general “mask available” sign justify restart.
| Trigger | Immediate action | Follow-up |
|---|---|---|
| Wheeze, cough or chest tightness linked to work | Stop uncontrolled exposure and signpost OH/medical advice. | COSHH and surveillance review. HSE ASTHMA |
| Symptoms improve on rest days or holiday | Treat as work-pattern signal. | Review asthmagen exposure. HSE ASTHMA |
| LEV or booth defect | Pause task if control depends on it. | Repair, test and verify. HSE ASTHMA |
| Tight-fitting RPE without a suitable face-fit test, or any RPE that is incompatible or defective | Do not rely on it for exposure control. | Select suitable RPE; face-fit test tight-fitting types. HSE ASTHMAHSE fit testing basics |
| High-level irritant exposure | Apply emergency and medical route. | Investigate and prevent repeat. HSE ASTHMA |
| Health surveillance concern | Use OH advice and protect confidentiality. | Check wider exposure group. HSE ASTHMA |
Asthma attack: act immediately
If the attack worsens, the reliever is not helping after its advised maximum, or no inhaler is available, call 999. Follow the person’s asthma plan and the call handler’s instructions; do not have the person drive themselves. Use current NHS asthma advice because reliever regimens differ. New work-pattern symptoms without emergency signs still need prompt clinical/OH advice and exposure-control review.
Where does occupational asthma prevention fail?
Prevention fails when asthmagens are not identified, symptoms are normalised, and RPE or training is used instead of controlling exposure at source.
A common failure is vague COSHH assessment. If the assessment says dust, fume or chemical but does not name the asthmagen, it is difficult to select controls or surveillance.
Another failure is late response. Occupational asthma can worsen if exposure continues after symptoms appear. Early symptom reporting and fast control review should be built into training and supervision.
A common near miss is treating early rhinitis or an evening cough as ordinary discomfort, especially when production still meets a dust or solvent target. The response is to test the process and worker pathway: identify the agent, inspect extraction and enclosure during real work, ask whether symptoms relate to shifts, and close the cause rather than merely reminding the worker to wear RPE. Replace dry sweeping with controlled cleaning, check extraction during the real task, and feed surveillance findings back into control decisions.
How do exposure controls and health surveillance connect?
Plan the surveillance response alongside exposure control, including symptoms reported between appointments. An occupational-health professional interprets health results; managers use the resulting work advice to correct the task.
This SHARE planning aid follows HSE G402 for GB. Use HSENI's separate NI route with a competent provider. Surveillance can detect harm; it does not make poorly controlled exposure acceptable. HSE G402 · HSENI health surveillance.
| Stage | Responsibility and evidence | Action connection |
|---|---|---|
| Assess exposure | Manager and assessor identify tasks, substances and exposed groups. | Prevent or control exposure; agree whether surveillance is required with the provider. |
| Plan the scheme | OH specifies baseline assessment before exposure and appropriate ongoing checks. | If a baseline was missed, arrange it promptly; the six-week example in G402 is not a grace period. |
| Between appointments | Worker knows the reporting route; any appointed responsible person is trained and supported by OH. | Refer reported symptoms promptly rather than waiting for the next scheduled check. |
| Interpret and respond | OH gives individual work advice and interprets similarly exposed group results. | Manager reviews assessment and controls, and implements advised work restrictions or alternative duties. |
| Confirm action | Manager records control corrections and restricted work advice; clinical details stay with appropriate confidential systems. | Check the revised work arrangement and resolve outstanding advice with OH. |
The provider decides the methods and frequency for the risk. A normal result is not permission to ignore control failures. Keep the existing urgent-care and GB/NI reporting routes available.
What evidence shows occupational asthma is being managed?
Good evidence shows that controls are planned, used, checked, corrected and reviewed.
Evidence should match the actual asthmagen and task. Higher-exposure spraying, dusty mixing or maintenance needs a traceable assessment, verified engineering controls, suitable surveillance and a response to symptoms; a generic health campaign is not control evidence.
Keep the product and task inventory, COSHH assessment, substitution decisions, LEV examination and maintenance, RPE selection and fit records, worker instruction, exposure monitoring where justified, and a restricted health-surveillance outcome and action trail. A manager should see the work restriction or control action needed, not an unnecessary clinical history. If one worker develops symptoms, compare the same task and controls for everyone exposed. The record should show who owns each defect, when the correction is due, and what observed evidence closed it.
How should occupational asthma be assured?
Assurance should test whether controls work in practice, not whether the page or procedure exists.
Assurance should include frontline checks, manager review and periodic independent sampling where risk warrants it. The purpose is to find weak signals early, close actions properly and update the risk assessment when work changes.
Sample actual mixing, spraying, cleaning and maintenance conditions, including shifts and contractors, against the written method. Check whether workers can report symptoms without retaliation, whether defects led to a hold, and whether the competent owner verified a correction before restart. A rising symptom pattern or repeated LEV fault should reach the manager who can change the process or fund replacement. Senior leaders should see unresolved high-risk actions and resource decisions, while a competent specialist checks complex design, measurement or health-surveillance questions.
Which duties apply in Great Britain and Northern Ireland?
Occupational asthma prevention rests on hazardous-substance assessment and control, suitable health surveillance where required, and prompt action on symptoms. Great Britain uses COSHH Regulations 2002 and RIDDOR 2013; Northern Ireland uses COSHH Regulations (NI) 2003 and RIDDOR (NI) 1997. Use the relevant regulator route for the work location.
A workplace exposure limit (WEL) is not a target for a sensitiser. A manager should ask whether source controls keep exposure as low as reasonably practicable and whether a competent person has checked the actual task. Health surveillance detects possible harm; it is not permission to continue uncontrolled exposure. Reporting a diagnosed case is a separate decision from responding to symptoms and protecting colleagues. HSE EMPLOYERS HSENI COSHH
| Jurisdiction | Legal route and decision | Evidence and boundary |
|---|---|---|
| Great Britain | COSHH Regulations 2002 require assessment and prevention or adequate control of hazardous-substance exposure. Use HSE guidance for asthmagens, suitable health surveillance and the relevant EH40 workplace exposure limit. | Document the agent, task, source controls and findings. HSE guidance is not itself the law; meet a limit and still reduce sensitiser exposure as far as reasonably practicable. HSE ASTHMAGENS HSE EMPLOYERS |
| Northern Ireland | COSHH Regulations (Northern Ireland) 2003 provide the separate NI control and surveillance route. HSENI references EH40 but the NI instrument and regulator govern the decision. | Use HSENI guidance and check current NI provisions and applicable limits before legal reliance; do not cite GB COSHH as the NI regulation. HSENI COSHH HSENI LUNG |
| Great Britain reporting | RIDDOR 2013 can require reporting occupational asthma when a diagnosis and significant or regular work exposure to a known respiratory sensitiser meet its criteria. | Use HSE occupational-disease guidance; a symptom alone is not the reportable diagnosis. HSE RIDDOR |
| Northern Ireland reporting | RIDDOR (Northern Ireland) 1997 has its own disease-reporting route; HSENI includes occupational asthma with significant or regular exposure to a known respiratory sensitiser. | Follow the NI report route after written medical notification and the applicable conditions; do not use the GB 2013 instrument. HSENI RIDDOR |
| United Kingdom data protection | UK GDPR and the Data Protection Act 2018 govern workers’ health information. | Keep clinical detail restricted and share only work-control advice needed by managers. GOV.UK personal data an employer may keep |
How should management arrangements verify controls?
Assign an owner, involve workers, check the control in use and act on failures before returning to routine work.
HSE’s Plan, Do, Check, Act guidance provides the government management route for this topic. Apply it to the actual task, equipment, people and jurisdiction, then keep the verification and corrective-action record. Standards-specific claims are held until their rights and competent review are resolved. HSE Plan, Do, Check, Act
What training and competence are needed?
Learning must match the task and the decision. A baker should demonstrate low-dust handling and a stop for failed extraction; a sprayer should know the assessed booth, air-fed protection and clearance rule; a supervisor must know how to hold work and seek competent health and hygiene advice. A general awareness session does not authorise those tasks.
Assess performance on the actual method and keep an authorisation or competence record proportionate to risk. Reassess after a product or process change, a defect, symptoms or poor practice; do not invent a universal certificate expiry. Training supports source control and cannot compensate for a leaking booth or an open dusty process.
| Role | Learning and practical test | Assessor and evidence | Reassessment trigger |
|---|---|---|---|
| Nearby staff and new starters | Recognise dust/mist releases, early symptoms and the reporting route. Awareness does not authorise hazardous tasks. | Supervisor checks a scenario; briefing and response record remain. | New agent, changed site or missed signal. |
| Bakers, sprayers and other operators | Identify the actual asthmagen, use the assessed enclosure/LEV/RPE and stop for defect or symptom. | Competent supervisor observes actual task and checks product and control knowledge; authorisation record remains. | Product, booth, equipment or method changes. |
| Maintenance and contractors | Isolate equipment, avoid secondary release during cleaning or repair and hand back with control checks. | Competent maintenance lead checks method and practical hand-back; work record remains. | Defect, modification or contractor change. |
| Supervisors and managers | Challenge a weak COSHH assessment, hold uncontrolled work, respond privately to symptoms and commission competent advice. | Safety/technical lead assesses a scenario and control decision; action and restart record remain. | Symptom, failed control, audit or changed process. |
| Hygienists, OH and auditors | Design exposure or surveillance checks within competence and trace source-control decisions without sharing unnecessary health details. | Professionally competent lead reviews sample plan, referral or audit; restricted specialist record remains. | New evidence, abnormal finding or unresolved trend. |
How could BuildOut Ltd manage this in practice?

BuildOut Ltd can manage occupational asthma by identifying asthmagens, controlling dust and fume at source, and responding quickly to symptom patterns.
In this contractor, workers may encounter wood dust, isocyanates, solder flux, cleaning chemicals and construction dust across changing sites.
Before a joinery job, BuildOut Ltd identifies the wood species, cutting and sanding steps, other trades nearby and an extraction method. During work the supervisor checks the extractor and housekeeping; dust escaping into the shared corridor is a stop point. A cleaner or contractor must receive the same exposure information. At hand-back, the team checks the area, records any defect and refers work-linked symptoms through the clinical route while reviewing other exposed tasks. This is an illustrative company method, not a separate legal rule.
| Management element | How the business would manage it | Evidence to review |
|---|---|---|
| Identify | Asthmagens are named in COSHH assessments. | Asthmagen register. HSE EMPLOYERS |
| Control | Substitution, LEV, cleaning and RPE standards are specified. | Task control standard. HSE EMPLOYERS |
| Health | Surveillance and symptom routes are clear. | OH programme. HSE EMPLOYERS |
| Assure | LEV, RPE, training and symptoms are reviewed. | Assurance dashboard. HSE EMPLOYERS |
How can the hierarchy of controls reduce risks while charging flour into a bakery mixer?
How can the ERICPD hierarchy of controls reduce risks while charging flour into a bakery mixer?

| Control level | Control for this activity | Owner and verification | Stop / restart decision |
|---|---|---|---|
| Eliminate | Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible. | Task owner verifies that the proposed change removes the named hazardous step, including foreseeable cleaning, maintenance and work transferred elsewhere. | If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls. |
| Reduce, including substitution | Validate a suitable low-dust flour or improver form while checking allergenic, skin, quality and process hazards. | Competent task/process owner validates suitability, compatibility and new hazards against the actual operating requirements before the alternative is adopted. | Reject an alternative if its performance is unproved or its new hazards are unresolved. |
| Isolate | Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work. | Supervisor checks the actual boundary, affected people and connected work; verify separation or isolation before allowing access. | Hold or stop for failed extraction, damaged cover, uncontrolled flour cloud or changed material not assessed. |
| Control: physical safeguards | Provide effective capture and suitable mixer covers or contained charging; use dust-controlled cleaning instead of dry sweeping. | Competent equipment/process owner checks flour/improver identity, charging height, capture, mixer cover and cleaning effectiveness. | Hold or stop for failed extraction, damaged cover, uncontrolled flour cloud or changed material not assessed. |
| Control: work method and response | Use a low-release charging method and realistic quantities; include maintenance, exposure review and required health surveillance in the plan. | Supervisor confirms the work limits, competent cover, communication and stop/restart authority with the people doing this activity. | Hold work when the agreed limits, competent cover or effective communication cannot be maintained. |
| PPE | Select adequate suitable RPE for remaining exposure and required fit evidence. A mask does not correct failed extraction or an open uncontrolled dust cloud. | Assessor confirms whether personal protection is needed and checks suitability, condition, compatibility and any required fit evidence. | Do not use unsuitable protection or rely on PPE to continue after an essential source control fails. |
| Discipline | Check capture and covers before use and after recipe or throughput changes; investigate respiratory reports and verify corrective action. | Release only after bakery owner accepts a validated method and effective source controls. Retain verification and unresolved restrictions at handover. | Keep the task on hold until required reinstatement evidence and unresolved defects are accepted by the responsible owner. |
How can the ISO 45001 hierarchy of controls reduce risks while charging flour into a bakery mixer?

| Control level | Control for this activity | Owner and verification | Stop / restart decision |
|---|---|---|---|
| Elimination | Use a suitable supplied dough or a contained supply arrangement that removes local open bag emptying where feasible. | Task owner verifies that the proposed change removes the named hazardous step, including foreseeable cleaning, maintenance and work transferred elsewhere. | If the hazardous step remains, keep it within the task assessment and select the stronger feasible remaining controls. |
| Substitution | Validate a suitable low-dust flour or improver form while checking allergenic, skin, quality and process hazards. | Competent task/process owner validates suitability, compatibility and new hazards against the actual operating requirements before the alternative is adopted. | Reject an alternative if its performance is unproved or its new hazards are unresolved. |
| Engineering controls | Enclose or segregate charging and keep other workers away from the release; prevent dust spreading into clean work. | Supervisor checks the actual boundary, affected people and connected work; verify separation or isolation before allowing access. | Hold or stop for failed extraction, damaged cover, uncontrolled flour cloud or changed material not assessed. |
| Engineering controls | Provide effective capture and suitable mixer covers or contained charging; use dust-controlled cleaning instead of dry sweeping. | Competent equipment/process owner checks flour/improver identity, charging height, capture, mixer cover and cleaning effectiveness. | Hold or stop for failed extraction, damaged cover, uncontrolled flour cloud or changed material not assessed. |
| Administrative controls | Use a low-release charging method and realistic quantities; include maintenance, exposure review and required health surveillance in the plan. | Supervisor confirms the work limits, competent cover, communication and stop/restart authority with the people doing this activity. | Hold work when the agreed limits, competent cover or effective communication cannot be maintained. |
| PPE | Select adequate suitable RPE for remaining exposure and required fit evidence. A mask does not correct failed extraction or an open uncontrolled dust cloud. | Assessor confirms whether personal protection is needed and checks suitability, condition, compatibility and any required fit evidence. | Do not use unsuitable protection or rely on PPE to continue after an essential source control fails. |
| Administrative controls | Check capture and covers before use and after recipe or throughput changes; investigate respiratory reports and verify corrective action. | Release only after bakery owner accepts a validated method and effective source controls. Retain verification and unresolved restrictions at handover. | Keep the task on hold until required reinstatement evidence and unresolved defects are accepted by the responsible owner. |
What do the acronyms and key terms mean?
These terms help readers distinguish the disease, exposure controls and separate GB and NI legal routes.
| Acronym | Meaning | Plain-English use |
|---|---|---|
| COSHH | Control of Substances Hazardous to Health | Hazardous-substance control: GB 2002 regulations and separate NI 2003 regulations. |
| EH40 | Workplace Exposure Limits guidance | HSE publication listing many workplace exposure limits used with COSHH assessments. |
| GP | General Practitioner | A doctor in primary care who can assess, advise, treat or refer. |
| HSE | Health and Safety Executive | Great Britain workplace health and safety regulator. |
| HSWA | Health and Safety at Work etc. Act 1974 | The core general work-safety statute for Great Britain; Northern Ireland uses the 1978 Order. |
| LEV | Local Exhaust Ventilation | Engineered extraction that captures contaminants close to source. |
| MHSWR | Management of Health and Safety at Work Regulations 1999 | GB risk-assessment regulations; Northern Ireland has separate 2000 management regulations. |
| OH | Occupational Health | Competent health advice focused on work impact, fitness, restrictions, adjustments and prevention. |
| PPE | Personal Protective Equipment | Equipment worn as a last line of protection. |
| RIDDOR | Reporting of Injuries, Diseases and Dangerous Occurrences Regulations | Disease reporting: 2013 regulations in Great Britain; 1997 regulations in Northern Ireland. |
| RPE | Respiratory Protective Equipment | Respiratory protection used where inhalation exposure remains after higher-level controls. |
| WEL | Workplace Exposure Limit | A substance-specific exposure limit; apply the GB EH40 or NI COSHH route as appropriate and still control sensitisers at source. |
| GB | Great Britain | England, Scotland and Wales; HSE is the principal workplace regulator. |
| NI | Northern Ireland | Separate health-and-safety instruments and the HSENI regulator route. |